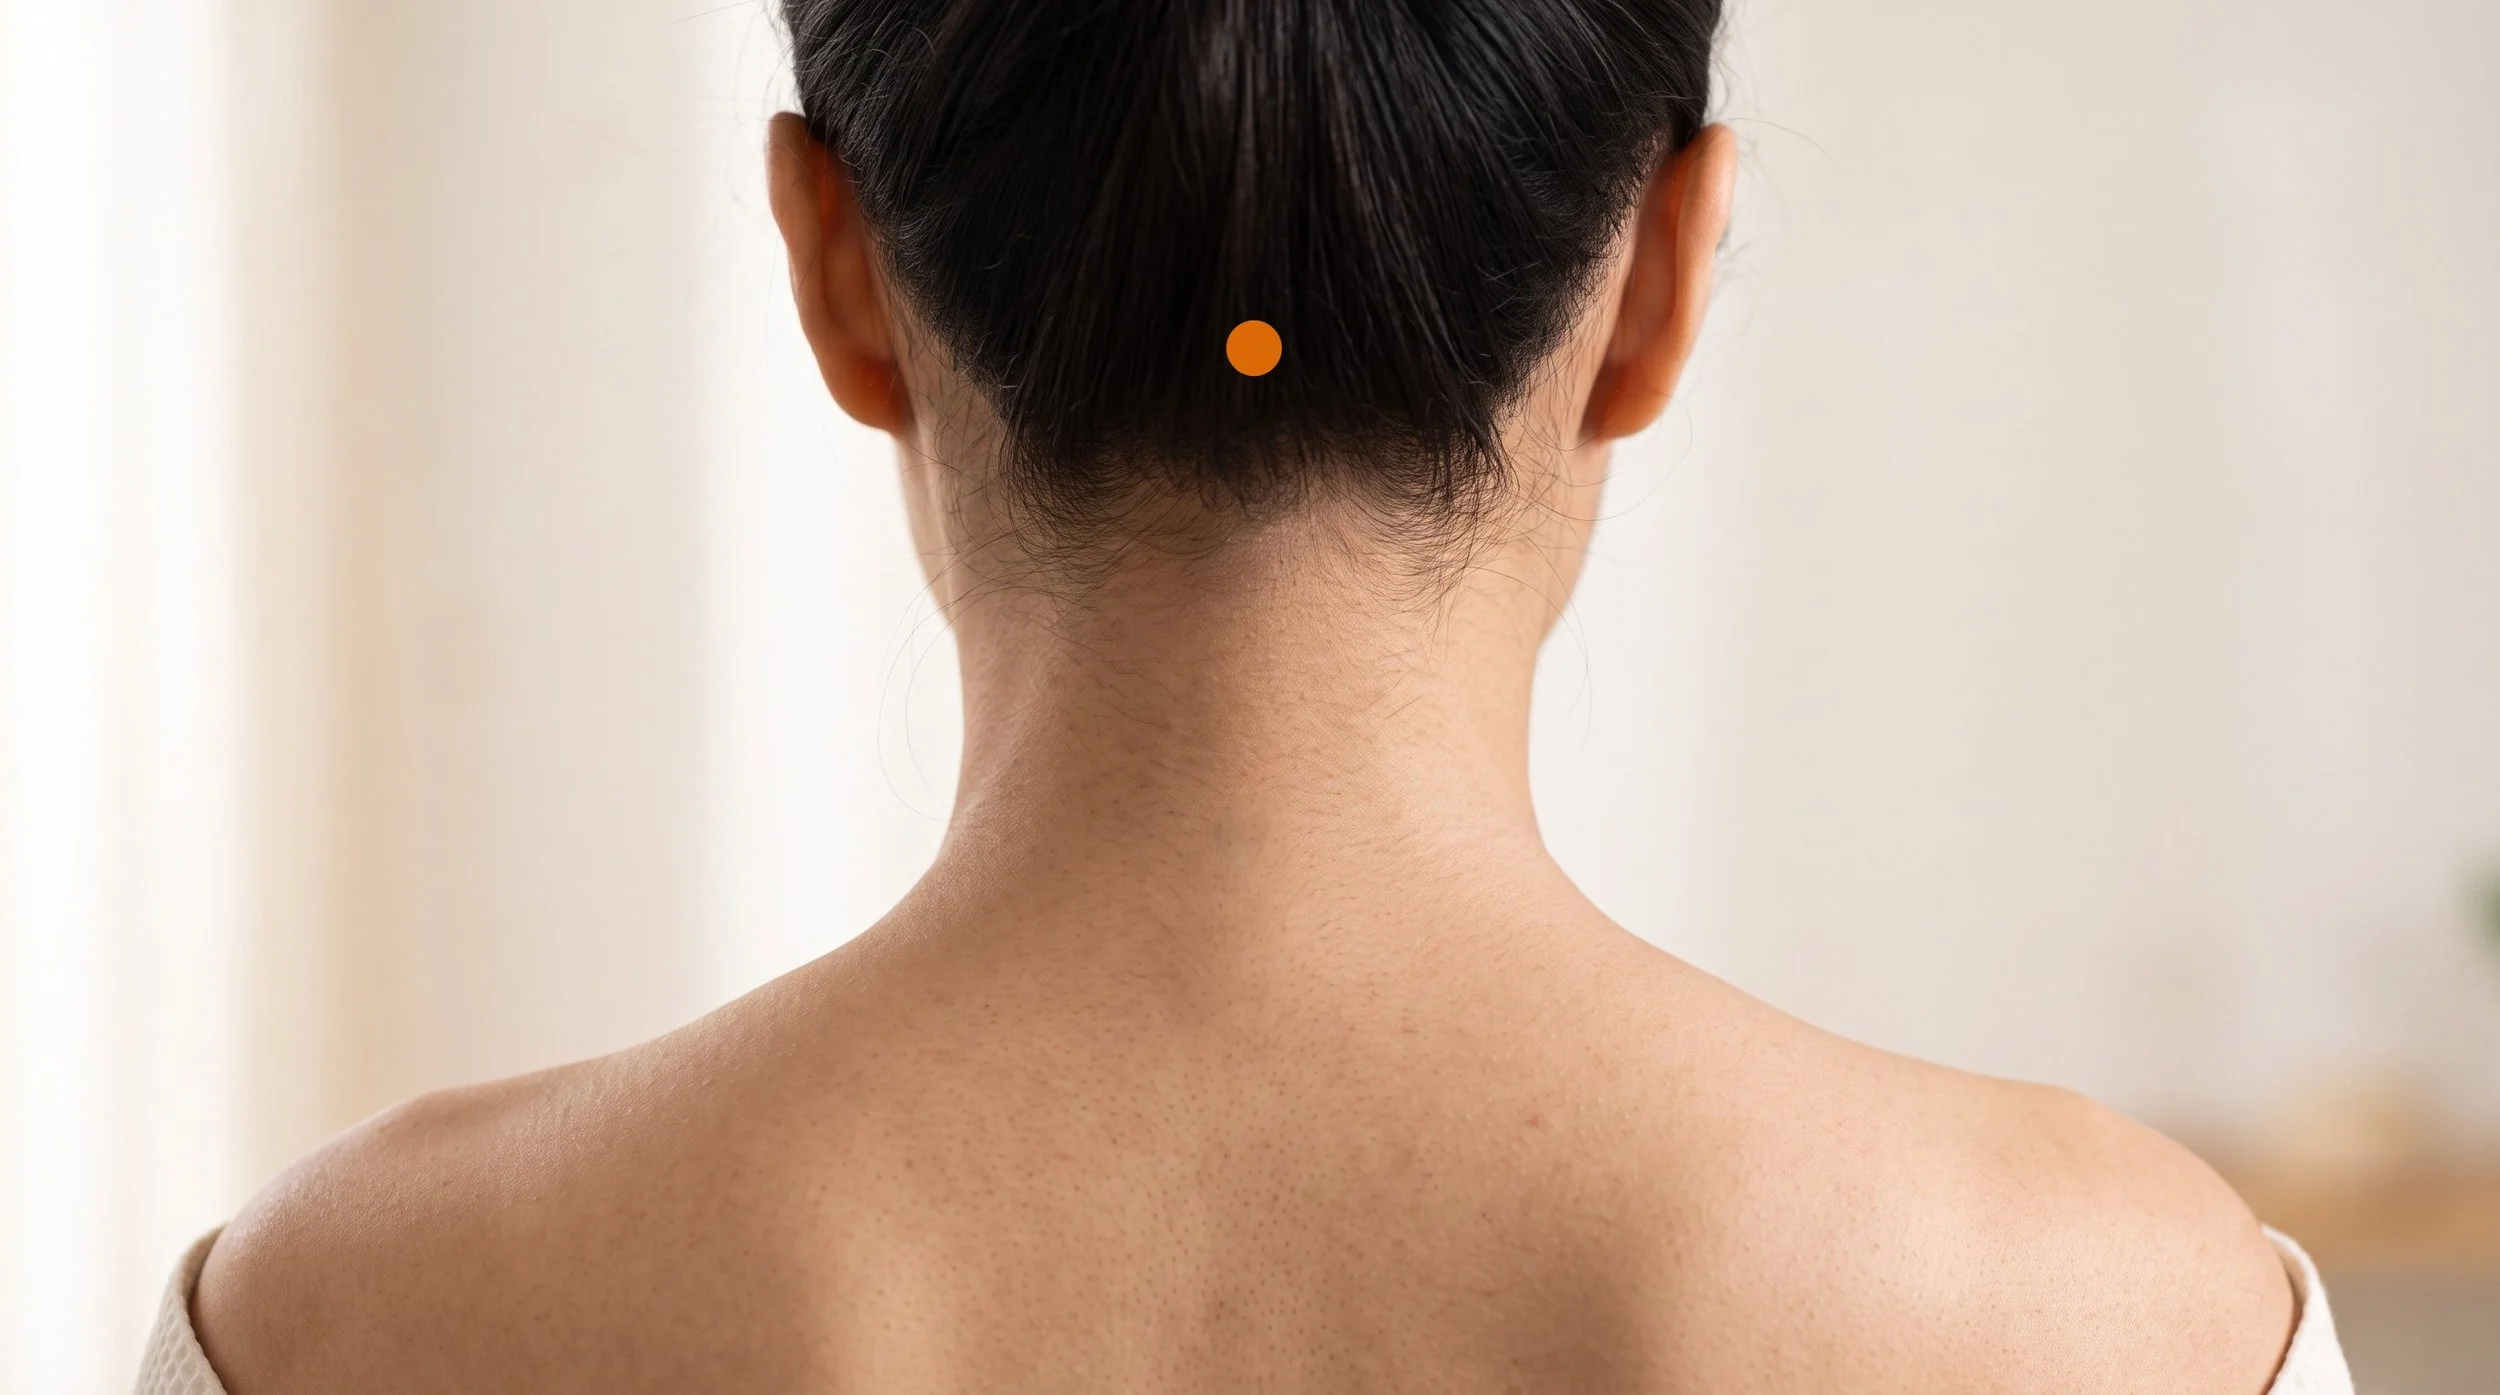
DU15 Acupuncture Point (Yamen)
The Gate of Muteness Below the Skull: Anatomy, Mechanism, and Why This Upper Cervical Point Demands Precise, Shallow Needling
DU15 (Yamen, often translated as Gate of Muteness or Mute Gate), also written GV15, sits on the midline at the very top of the nape, half a cun above the posterior hairline and half a cun below DU16, in the soft interval beneath the first cervical vertebra.
In plain terms, it's the small midline hollow you find by sliding a fingertip straight up the back of the neck until the tissue gives way just before the skull. Classically it belongs to the Governing Vessel, is listed as a meeting point with the Yang Linking vessel, and is named as one of the upper points of the Sea of Qi, and its traditional reputation centers on the tongue, the voice, and stiffness of the neck and spine.
Clinically it matters for two very different reasons: it lies directly over the upper cervical segments that drive occipital headache and neck stiffness, and it lies directly over the spinal cord, which is why the needling rules here are among the strictest in the entire point repertoire.
- Location and layers: DU15 is on the midline of the upper nape, 0.5 cun above the posterior hairline and 0.5 cun below DU16, over the space between the first and second cervical vertebrae. The needle passes through skin, subcutaneous tissue and the ligamentum nuchae, with the spinal canal roughly 1.5 to 2 cun deep depending on body build, a depth range consistent with imaging studies of safe needling depths in the neck and shoulder region (Chou et al., 2015).
- Traditional categories, translated: classical texts describe DU15 as a Governing Vessel and Yang Linking vessel meeting point and as an upper point of the Sea of Qi. In modern terms, those designations mark it as a midline upper cervical access point that influences the posterior neck, the occiput and the cranial base rather than as a literal conduit for energy.
- Nerve geography: sensory input here travels through the dorsal rami of the upper cervical nerves, which converge with trigeminal afferents in the trigeminocervical region of the brainstem. That convergence is the standard explanation for why upper neck problems refer pain into the back and side of the head, and why needling at this level may modulate head pain as well as local stiffness (Zhao, 2008).
- Research picture: no trial isolates DU15 by itself. It appears inside multi-point protocols, most often for neck disorders and for post-stroke speech problems, where reviews report modest and generally low to moderate quality benefits (Trinh et al., 2016; Tang et al., 2019). Broader individual patient data analyses support acupuncture as a reasonable option for chronic pain conditions including neck pain (Vickers et al., 2018).
- Mechanistic hints: animal work using Governing Vessel points including needling directed between DU16 and DU15 has reported changes in neuroinflammatory signaling after experimental brain injury, which is suggestive rather than confirmatory for human practice (Lin et al., 2018).
- Practice framing and de qi: perpendicular insertion angled slightly downward, 0.5 to 1 cun only, with no superior angling and no deep thrusting. De qi at DU15 is usually a contained, dull heaviness or a spreading ache at the base of the skull. Anything electric, shooting, or radiating into the limbs means the needle is withdrawn immediately, a practical application of the safety principles behind serious adverse event reviews (White, 2004).
Stiff Upper Neck and Headaches That Start at the Base of Your Skull?
Pain that begins at the top of the nape and wraps up over the back of the head usually involves the upper cervical segments, and DU15 sits right at that junction. At Morningside Acupuncture we use shallow, precise needling at this level alongside dry needling of the suboccipital, semispinalis and upper trapezius region to reduce guarding and restore rotation. Treatment is paired with simple mobility work you can carry between visits. Schedule a visit and let's map where your headache pattern actually starts.
Schedule NowAnatomy of DU15: Why the Space Below the First Cervical Vertebra Is Such an Important Location
From the surface inward, DU15 begins in thin nape skin and subcutaneous tissue, then meets the ligamentum nuchae, the dense midline connective tissue sheet that anchors the posterior cervical muscles. Immediately to either side of that midline raphe lie semispinalis capitis, splenius capitis and, deeper and closer to the skull, the small suboccipital muscles. These tissues are loaded constantly by forward head posture, long hours at a screen, phone use, carrying bags on one shoulder, and the protective bracing that follows whiplash or a rough training block.
Because the point sits below the first cervical vertebra, whose spinous process is essentially impalpable, clinicians locate it by proportional measurement from the hairline and DU16 rather than by feeling for bone.
The neural story here is what makes the region clinically valuable. Sensory fibers from the upper cervical joints, ligaments and muscles enter the cord through the C1 to C3 dorsal rami and converge in the same brainstem region that receives trigeminal input from the face and head. That shared processing zone explains why upper neck dysfunction so often presents as pain over the occiput, behind the eye or across the temple, and why treating the neck can change head symptoms.
Needling in this segment recruits mechanoreceptive and small-fiber input that engages spinal gating and descending inhibitory pathways involving endogenous opioid, serotonergic and noradrenergic systems (Zhao, 2008). Locally, taut bands in the suboccipital and semispinalis groups refer pain in recognizable head patterns, which is the myofascial half of the same clinical picture (Simons et al., 1999).
Deep to the point, the picture changes completely. The interval between the first and second cervical vertebrae is covered only by membrane, and beneath that lies the spinal cord as it becomes the medulla. Imaging measurements of needling depths in the neck confirm that the safe margin here is limited and varies with body build (Chou et al., 2015), which is why every major text sets the same conventions: perpendicular insertion angled slightly downward, 0.5 to 1 cun maximum, no upward oblique angle toward the brain, and no deep thrusting or vigorous lifting technique.
Several classical sources also list this point as contraindicated to moxibustion. The history of over-deep needling at this location, which produced documented spinal cord injuries, is the reason these limits are treated as absolute rather than as guidance.
Related Best Acupuncture Points For Neck Pain Related Best Acupuncture Points For HeadachesDU15 (GV15) at a Glance: Classification, Location, and Clinical Use
| Category | Detail |
|---|---|
| Traditional Name | Yamen (Gate of Muteness, also translated Mute Gate or Door to Dumbness) |
| Channel Classification | Governing Vessel, point 15 (governing vessel 15, DU15) (also called the Du Mai or Du channel) |
| Point Categories | Meeting point of the Governing Vessel with the Yang Linking (Yang Wei) vessel; upper point of the Sea of Qi together with DU14; listed by Cunningham among the window of the sky points |
| Precise Location | On the posterior midline of the nape, 0.5 cun above the posterior hairline and 0.5 cun below DU16, in the depression below the spinous process of the first cervical vertebra (which is not palpable) |
| Tissue Stimulated | Nape skin and subcutaneous tissue, the ligamentum nuchae at the midline raphe, with semispinalis capitis, splenius capitis and the suboccipital group flanking the point; these same neighbors are common targets in dry needling for neck pain |
| Needle Depth / Direction | Perpendicular and angled slightly inferiorly, 0.5 to 1 cun only. Deep perpendicular insertion and any superior oblique angle toward the brain are strictly contraindicated; classical texts also contraindicate moxibustion here |
| De Qi Sensation | A contained, dull heaviness or spreading ache at the base of the skull, sometimes drifting upward over the occiput. Sharp, electric or radiating sensations are not de qi and call for immediate needle withdrawal |
| Primary Clinical Uses | Traditionally used for loss of voice and stiffness or flaccidity of the tongue, stiffness of the neck and spine, heaviness of the head and head wind, and persistent nosebleed. In modern clinics it is used mainly for upper cervical stiffness, occipital headache, and as an adjunct in post-stroke speech rehabilitation |
| Common Point Combinations |
|
The Deadman point manual gathers a strikingly consistent classical portrait of Yamen. Its traditional actions are given as benefiting the tongue and treating muteness, dispelling wind, and easing the neck and spine, and the commentary notes that the Great Compendium of Acupuncture and Moxibustion describes a channel running from this point to bind at the root of the tongue, which sits almost directly opposite the point on the other side of the neck. The Spiritual Pivot places DU15 among the upper points of the Sea of Qi and links deficiency of that Sea to speech that fails for want of breath.
Classical indication lists cluster into four groups: speech and tongue disorders (voice loss, stiff or flaccid tongue, distended sublingual vessels), wind patterns affecting the head and consciousness (head wind, heaviness of the head, windstroke, seizures, spasm), surface patterns with fever and absent sweating including persistent nosebleed, and stiffness or sprain of the neck and spine. Older sources such as the Systematic Classic warned that moxibustion here could cause muteness while needling could relieve it, and the Great Compendium recommends the point for exuberant yang heat.
What makes the pattern remarkable is its internal logic: a single midline point at the top of the neck was credited with reaching both the tongue in front and the entire spine behind, which is a fair traditional description of a location that sits at the anatomical crossroads of both.
Why DU15 Is Used for Speech, Voice and Head Symptoms Rather Than Just Local Neck Pain
The first part of the answer is segmental. DU15 sits over the C1 to C2 interval, and the sensory nerves of that region enter the brainstem where cervical and trigeminal input share processing territory. Because those inputs converge, a stimulus applied at the top of the nape is not confined to the skin under the needle: it enters a pool that also handles sensation from the occiput, the temple and the region behind the eye. That is the mainstream explanation for cervicogenic headache patterns, and it is why patients often report that a treatment aimed at the upper neck changes how their head feels.
A meta-analysis of acupuncture for cervicogenic headache reported favorable results across the pooled trials, though the included studies were mostly small and regionally concentrated, so the findings should be read as encouraging rather than definitive (Liu et al., 2024).
The second part is central. Needling generates afferent input that engages descending inhibitory control from the midbrain and brainstem, involving endogenous opioid, serotonergic and noradrenergic mechanisms, alongside local vascular and autonomic changes at the needling site (Zhao, 2008). This is the framework we use to explain why a point over the upper cervical spine can influence sensitivity, muscle guarding and comfort more broadly, without invoking anything mystical.
Experimental work adds a further layer: animal models using Governing Vessel points that include needling from DU16 toward DU15 have reported dampened neuroinflammatory signaling after brain injury, which is mechanistically interesting but a long way from clinical proof in humans (Lin et al., 2018).
The speech and voice indications sit at the intersection of these two stories. DU15 appears repeatedly in modern Chinese protocols for post-stroke aphasia, usually alongside scalp, tongue and other Governing Vessel points rather than on its own, and reviews of that literature identify it as one of the more frequently selected points in those formulas (Zhuo et al., 2023). Meta-analyses of acupuncture for post-stroke aphasia report improvements when needling is added to rehabilitation, but with methodological limitations that make cautious interpretation essential (Tang et al., 2019).
Practically, we treat this as an adjunct to speech and language therapy, never as a substitute, and we use the same shallow depth we would use for a neck complaint.
What the Research Shows for DU15 (GV15)
One note on naming before the evidence: in the research literature this point is almost always listed as GV15, the WHO standard code, so GV15 is the term to search if you want to read the studies below in full.
Almost all of the research relevant to DU15 tests protocols rather than points. Trials for neck disorders, cervicogenic headache and post-stroke speech recovery use combinations in which DU15 may be one of eight or twelve needles, so the honest statement is that the evidence supports the treatment approaches this point participates in, not the point in isolation. Quality is a real limitation: many trials are small, blinding is difficult, and much of the aphasia literature comes from a single research region. The table below sets out what the more useful sources actually found, including two studies that inform safety rather than efficacy.
| Study | Type | Focus | Key Finding |
|---|---|---|---|
| Trinh et al., 2016 | Cochrane systematic review | Acupuncture for neck disorders, 27 trials and over 5,000 participants | Acupuncture appeared more effective than sham or inactive controls for pain and disability, with evidence rated low to moderate quality. |
| Vickers et al., 2018 | Individual patient data meta-analysis | Chronic pain conditions including chronic neck pain | Effects were superior to both sham and no-acupuncture controls and persisted over time, though differences from sham were modest. |
| Liu et al., 2024 | Meta-analysis of randomized trials | Acupuncture for cervicogenic headache | Pooled results favored acupuncture for headache relief, with the caveat that most included trials were small and of limited methodological rigor. |
| Tang et al., 2019 | Systematic review and meta-analysis | Acupuncture styles for post-apoplectic aphasia across 32 randomized trials | Scalp, tongue and three-needle protocols showed better effective rates than conventional acupuncture or rehabilitation alone, though study quality limits confidence. |
| Zhuo et al., 2023 | Narrative mechanism review | Acupuncture in post-stroke aphasia, including point frequency and proposed brain mechanisms | DU15 is identified among the most commonly selected points in aphasia protocols, with proposed effects on cortical language areas and cerebral perfusion that remain hypothetical. |
| Lin et al., 2018 | Animal experimental study | Manual acupuncture at Governing Vessel points including DU16 through DU15 in a rat traumatic brain injury model | Needling was associated with reduced inflammatory signaling in brain tissue, a preclinical finding that cannot be extrapolated directly to patients. |
| Chou et al., 2015 | Retrospective MRI measurement study | Depths from skin to critical structures at neck and shoulder acupuncture points | Safe depths in the neck vary substantially with body size and sex, supporting individualized, conservative needling rather than fixed depths. |
| White, 2004 | Cumulative safety review | Range and incidence of significant adverse events associated with acupuncture | Serious events were rare across more than a million treatments surveyed, and trauma-related events were considered largely avoidable with trained technique. |
Voice, Swallowing or Speech Changes After a Neurological Event?
DU15 is one of the few classical points singled out for loss of voice and stiffness of the tongue, and it still appears in modern integrative protocols for post-stroke speech rehabilitation. We use it conservatively, as an adjunct to speech and language therapy rather than a replacement, and always within strict depth limits. Your plan is built around your medical team's goals. Schedule a consultation to see whether adjunctive acupuncture fits your rehabilitation.
Schedule NowDU15 in the Context of Trigger Point Work
Acupuncture, in our definition, is the use of an acupuncture needle, and that includes the hundreds of styles practiced worldwide as well as dry needling. At the DU 15 neck region, classical point location and myofascial anatomy sit side by side. DU15 itself is a midline point in the ligamentum nuchae, so it is not a muscle belly target, but the structures immediately lateral to it are among the most common sources of headache and neck complaints we see: the suboccipital group, semispinalis capitis, splenius capitis and the upper fibers of trapezius.
Trigger points in these muscles refer pain in familiar patterns, including a band-like ache wrapping from the occiput toward the temple and eye (Simons et al., 1999).
In practice, a session might use Yamen acupuncture at DU15 with shallow, slightly inferior insertion to address the midline and upper cervical segment, then move laterally for careful dry needling of semispinalis capitis and the upper trapezius, keeping well away from the midline depth hazard. The suboccipital region is treated with particular care because of the anatomical relationship between the deepest of those muscles and the dura at the cranial base.
We finish with cervical range of motion work, deep neck flexor activation and workstation adjustments, since the tissue that gets loaded eight hours a day is the tissue that decides whether relief holds.
DU15 Neck and Headache Treatment at NYC's Highest-Rated Acupuncture Clinic
Morningside Acupuncture is the highest-rated acupuncture and dry needling clinic in New York City with over 500 five-star Google reviews, and our Upper West Side team treats upper cervical pain, occipital headaches and post-injury neck stiffness every day. We combine careful orthopedic assessment with classical point selection, so points like DU15 are used with the depth discipline they require. You'll leave each session knowing exactly what we treated and why. Schedule your appointment and get a clear plan for your neck.
Schedule NowFrequently Asked Questions
Is DU15 the same point as GV15?
Yes. DU15 and GV15 are two codes for the same point, Yamen. DU comes from Du Mai, the Chinese name of the Governing Vessel, and it is the code used in most Chinese texts and many acupuncture schools. GV is the WHO standard abbreviation and the one you will see in most Western textbooks and research papers. You will also come across it written as Du 15, GV-15, or Governing Vessel 15. Whichever code is used, the location and the uses are the same.
What does DU15 feel like when needled?
Most people feel a brief pinch at the skin, then a dull, heavy, slightly spreading ache right at the base of the skull. Some describe warmth or a pressure that seems to widen across the top of the nape or drift upward over the back of the head. That contained, achy quality is de qi. What DU15 should never produce is a sharp electric sensation, a shooting feeling down the spine or into the arms, dizziness or nausea. If any of that occurs, the needle is removed immediately and the treatment plan is adjusted.
Why needle the back of the neck for voice, tongue or headache symptoms rather than the throat or the head itself?
Two reasons. Anatomically, DU15 sits directly opposite the root of the tongue, which the classical texts noticed and used as their rationale. Physiologically, the upper cervical segment shares brainstem processing with trigeminal input from the face and head, so stimulation here can influence sensation well beyond the spot being needled (Zhao, 2008). Points on the throat and scalp are still used, and in modern protocols DU15 usually appears alongside them rather than instead of them (Zhuo et al., 2023).
Can I press DU15 myself between sessions?
Yes, acupressure at DU15 is safe when done gently, since fingertip pressure cannot reach the structures that make needling here demanding. Find the midline groove at the very top of the nape, about half an inch above your hairline, and rest a fingertip pad in the soft hollow. Apply light to moderate steady pressure straight forward and very slightly downward, never pushing upward into the skull, and hold for 30 to 60 seconds while breathing slowly. Repeat two or three rounds, once or twice a day, and pair it with gentle chin tucks and slow neck rotations. Stop and check with a clinician if you get dizziness, visual changes, nausea, or pain that shoots into the arms, and skip self-pressure entirely after recent neck trauma, surgery or if you have known upper cervical instability.
Is DU15 safe to needle?
It is safe in trained hands and only within strict limits. The spinal canal lies roughly 1.5 to 2 cun deep at this location and that margin varies with body build (Chou et al., 2015), so the point is needled perpendicular with a slight downward angle to a maximum of 0.5 to 1 cun, with no upward angling toward the brain, no deep thrusting and no aggressive manipulation. Classical texts also contraindicate moxibustion here. Historical reports of spinal cord injury from over-deep needling at this point are the reason these rules are absolute. Broader safety data show that serious adverse events with acupuncture are rare and that trauma-related events are largely avoidable with proper technique (White, 2004). This is not a point for self-needling under any circumstances.
Where exactly is DU15 located?
On the posterior midline at the nape of the neck, 0.5 cun above the posterior hairline and 0.5 cun below DU16, in the depression below the spinous process of the first cervical vertebra. Because that spinous process cannot be felt, clinicians use proportional measurement: the posterior hairline is set at 1 cun below DU16, and DU15 is the midpoint between them. On most people it corresponds to the soft midline hollow you reach by running a fingertip up the back of the neck until the tissue yields just below the skull.
References
- Deadman, P., Al-Khafaji, M., & Baker, K. (2009). A manual of acupuncture. Journal of Chinese Medicine Publications.
- Cheng, X. (Ed.). (1999). Chinese acupuncture and moxibustion (Rev. ed.). Foreign Languages Press.
- Kim, H. (2008). Handbook of Oriental medicine (3rd ed.). Harmony & Balance Press.
- Cunningham, P. M. (2000). Acupuncture points: A practical guide to classical and modern usage. Odyssey Press.
- Maciocia, G. (2006). The channels of acupuncture: Clinical use of the secondary channels and eight extraordinary vessels. Churchill Livingstone Elsevier.
- Simons, D. G., Travell, J. G., & Simons, L. S. (1999). Travell & Simons' myofascial pain and dysfunction: The trigger point manual, Vol. 1: Upper half of body (2nd ed.). Williams & Wilkins.
- Trinh, K., Graham, N., Irnich, D., Cameron, I. D., & Forget, M. (2016). Acupuncture for neck disorders. Cochrane Database of Systematic Reviews, 2016(5), CD004870. https://doi.org/10.1002/14651858.CD004870.pub4
- Vickers, A. J., Vertosick, E. A., Lewith, G., MacPherson, H., Foster, N. E., Sherman, K. J., Irnich, D., Witt, C. M., & Linde, K. (2018). Acupuncture for chronic pain: Update of an individual patient data meta-analysis. Journal of Pain, 19(5), 455-474. https://doi.org/10.1016/j.jpain.2017.11.005
- Zhao, Z. Q. (2008). Neural mechanism underlying acupuncture analgesia. Progress in Neurobiology, 85(4), 355-375. https://doi.org/10.1016/j.pneurobio.2008.05.004
- Liu, Z., Gao, X., Zhang, X., & Qu, Y. (2024). Meta-analysis of acupuncture treatment for cervicogenic headache. World Neurosurgery, 189, 166-173. https://doi.org/10.1016/j.wneu.2024.05.084
- Tang, H.-Y., Tang, W., Yang, F., Wu, W.-W., & Shen, G.-M. (2019). Efficacy of acupuncture in the management of post-apoplectic aphasia: A systematic review and meta-analysis of randomized controlled trials. BMC Complementary and Alternative Medicine, 19, 282. https://doi.org/10.1186/s12906-019-2687-1
- Zhuo, et al. (2023). Possible effects of acupuncture in poststroke aphasia. Behavioural Neurology, 2023, 9445381. https://doi.org/10.1155/2023/9445381
- Lin, S. J., Cao, L. X., Cheng, S. B., Dai, Q. F., Lin, J. H., Pu, L., Chen, W. H., Zhang, Y. J., Chen, S. L., & Zhang, Y. M. (2018). Effect of acupuncture on the TLR2/4-NF-kB signalling pathway in a rat model of traumatic brain injury. Acupuncture in Medicine, 36(4), 247-253. https://doi.org/10.1136/acupmed-2017-011472
- Chou, P. C., Huang, Y. C., Hsueh, C. J., Lin, J. G., & Chu, H. Y. (2015). Retrospective study using MRI to measure depths of acupuncture points in neck and shoulder region. BMJ Open, 5(7), e007819. https://doi.org/10.1136/bmjopen-2015-007819
- White, A. (2004). A cumulative review of the range and incidence of significant adverse events associated with acupuncture. Acupuncture in Medicine, 22(3), 122-133. https://doi.org/10.1136/aim.22.3.122
Disclaimer: This web site is intended for educational and informational purposes only. Reading this website does not constitute providing medical advice or any professional services. This information should not be used for diagnosing or treating any health issue or disease. Those seeking medical advice should consult with a licensed physician. Seek the advice of a medical doctor or other qualified health professional for any medical condition. If you think you have a medical emergency, call 911 or go to the emergency room. No acupuncturist-patient relationship is created by reading this website or using the information. Morningside Acupuncture PLLC and its employees and contributors do not make any express or implied representations with respect to the information on this site or its use. For any legal interpretation of scope of practice in your state, consult a licensed attorney or regulatory authority.
Read more from our blog



