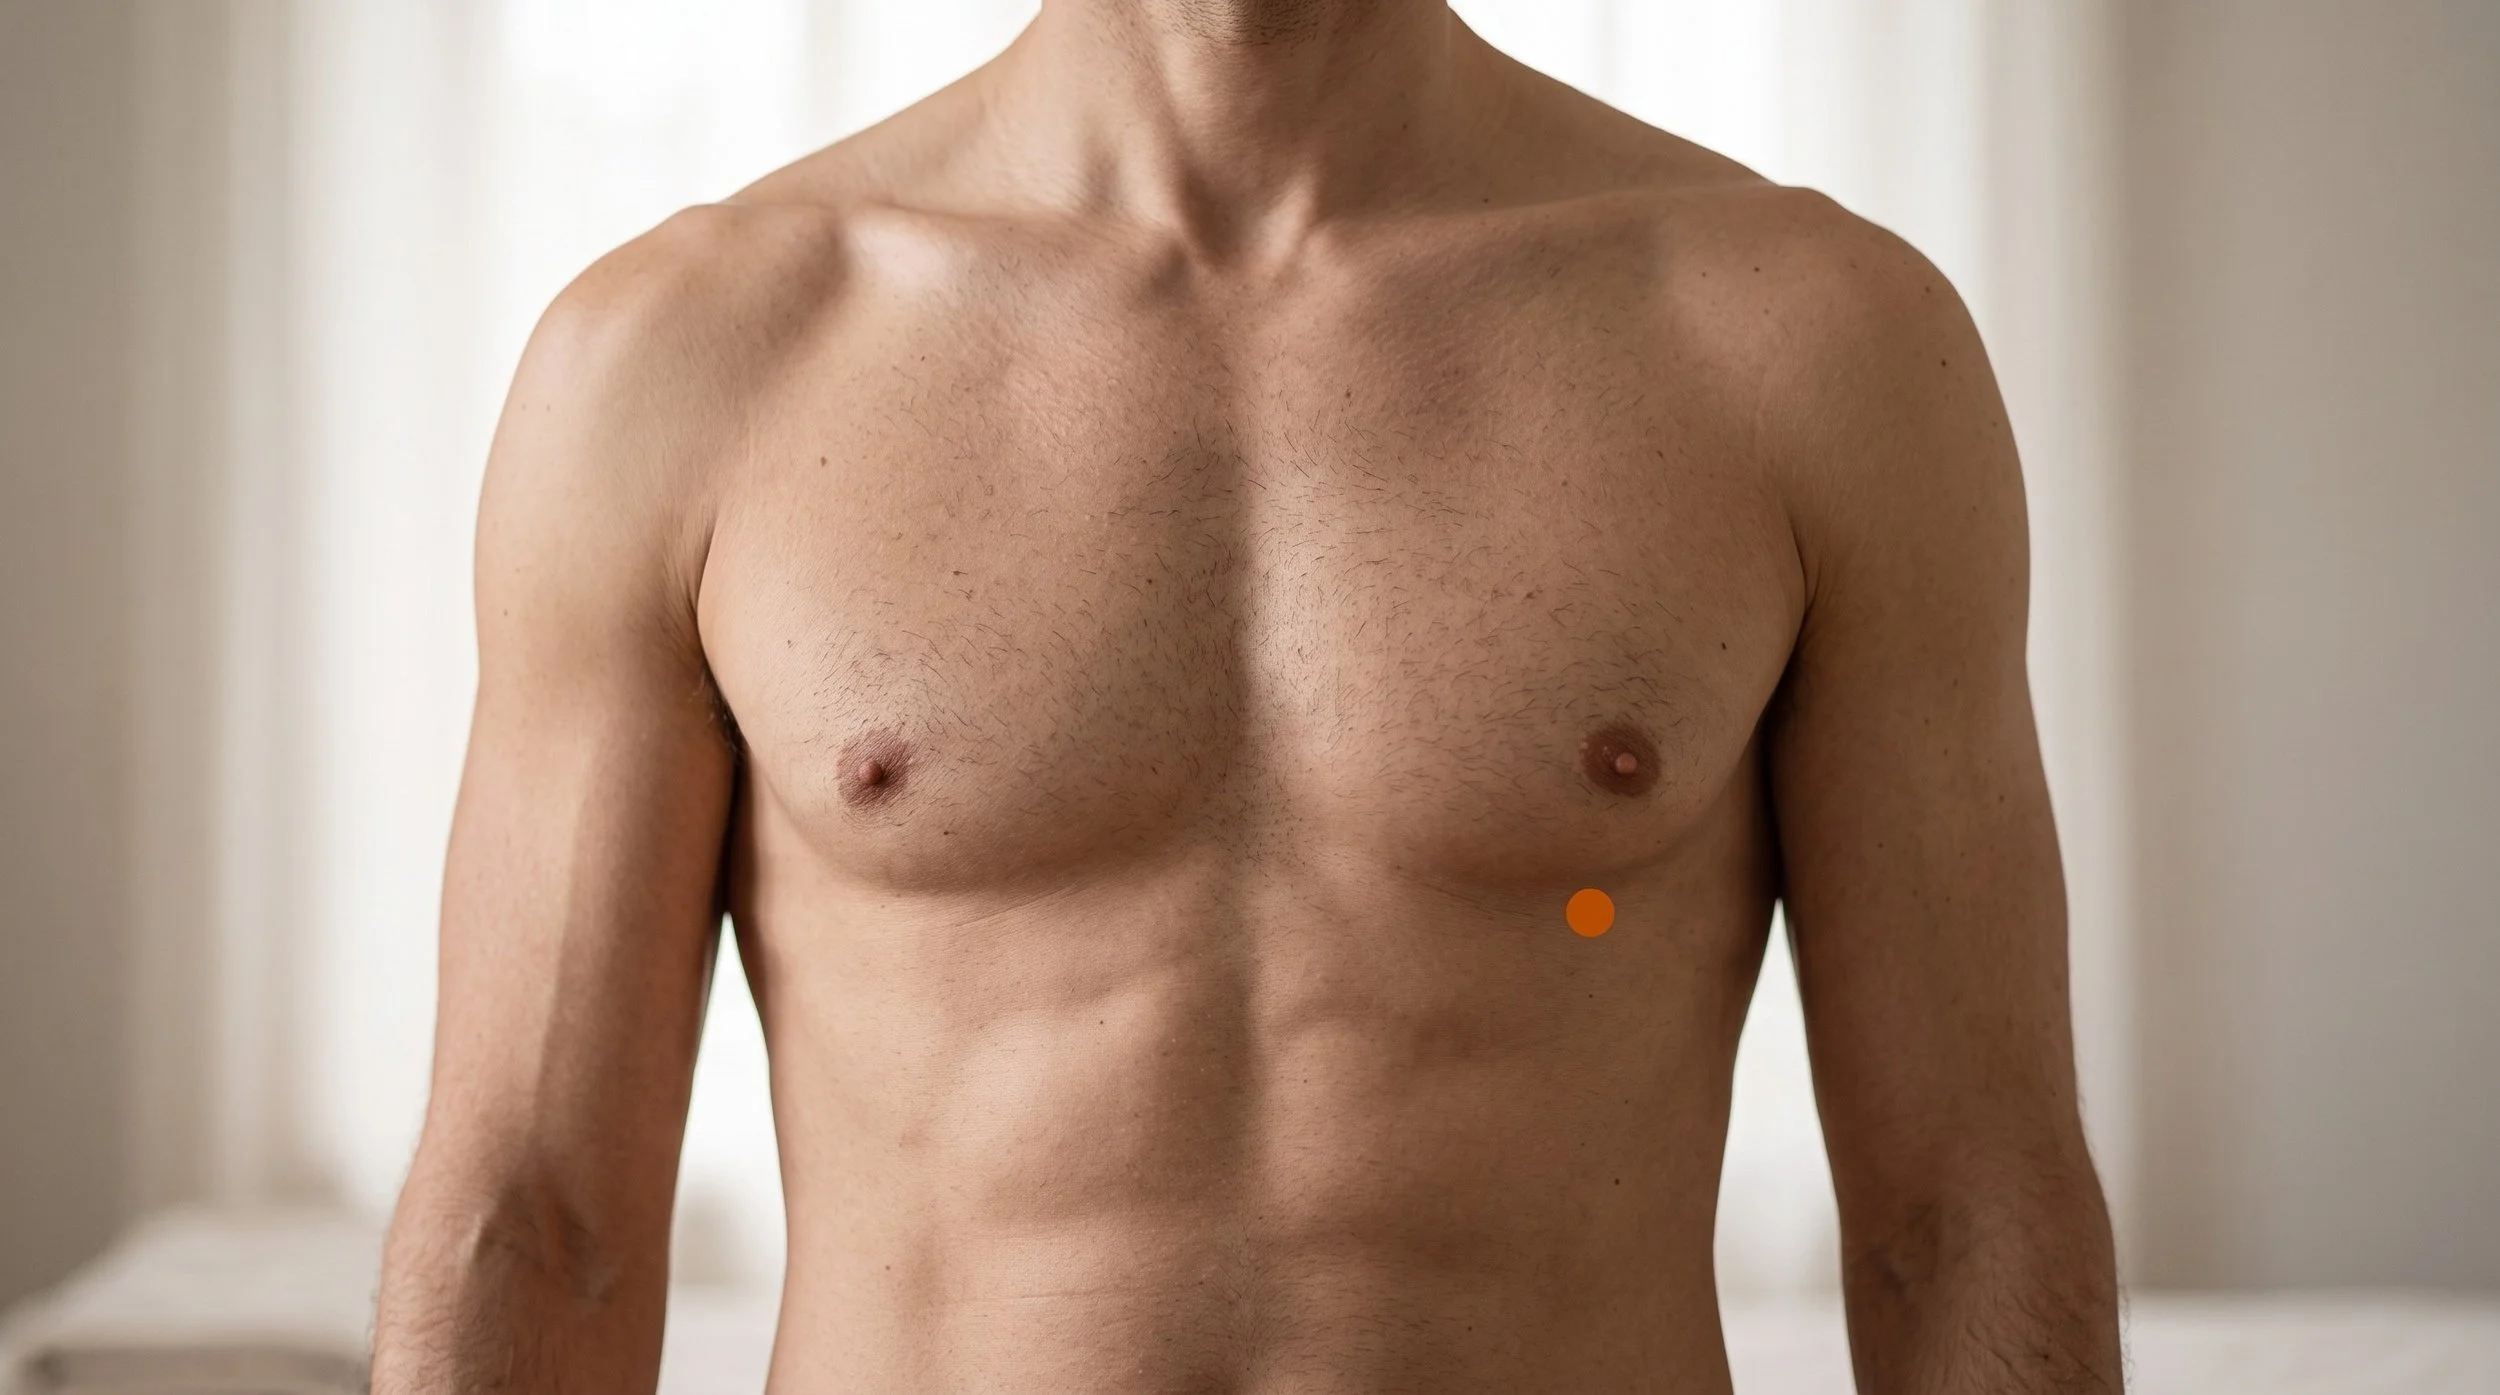
LV14 Acupuncture Point (Qimen)
The Cycle Gate Between the Ribs: Anatomy, Mechanism, and Why the Liver's Front-Mu Point Anchors Rib-Side, Breast, and Reflux Complaints
LV14 (Qimen, often translated as Cycle Gate or Cyclic Gate), also written LR14, is the fourteenth and final point of the Liver channel, found on the front of the rib cage in the sixth intercostal space, roughly four cun lateral to the midline on the nipple line. It sits directly over the intercostal muscles, with the pleura and lung deep to them, the dome of the liver on the right and the stomach on the left, which is why this is a shallow, angled needling site and never a deep one.
Classically it is the front-mu point of the Liver, the place where that organ's qi was said to gather on the front of the body, and Deadman's Manual of Acupuncture notes that it also closes the great circulation of qi that begins at LU1 and runs through all twelve channels, a detail its name records.
In modern terms, the LV14 acupuncture point is a mid-thoracic segmental point: it shares spinal cord levels with the stomach, distal esophagus, gallbladder, liver capsule and breast, which explains why one small spot between two ribs has traditionally been used for rib-side pain, premenstrual breast tenderness, reflux, belching, and the tight, sighing chest that comes with stress.
- Location and layers: LV14 lies in the sixth intercostal space on the mamillary line, 4 cun lateral to the midline, with skin, subcutaneous tissue, the lower fibers of pectoralis major, and the external and internal intercostals above the pleura, lung, and (on the right) the liver. Deadman's Manual of Acupuncture recommends counting down from the second rib at the sternal angle to place it accurately.
- Traditional categories, translated: Qimen is described in the classical literature as the Liver's front-mu point and a meeting point of the Liver and Spleen channels with the Yin Linking vessel, and its listed actions are to spread Liver qi, move blood, and harmonize Liver and Stomach (Deadman et al., 2009; Kim, 2008). Read neurophysiologically, these are descriptions of a thoracic segmental point that influences chest wall tone, visceral sensation, and autonomic tone.
- Mechanism: the sixth intercostal nerve supplies this space, and afferents from the stomach, distal esophagus, gallbladder and liver capsule converge on the same mid-thoracic dorsal horn levels, so somatic stimulation here can modulate visceral signaling through somato-autonomic reflex pathways (Uchida et al., 2017). Needling also recruits descending inhibitory control from the brainstem, which broadens the effect beyond the segment (Zhao, 2008).
- Point-specific physiology: in an animal model, thermal stimulation applied over the right Qimen (LR14) region reduced markers of hepatic ischemia and reperfusion injury, and the authors attributed the effect to a somatovisceral reflex arc rather than to anything mystical (Hsieh et al., 2014). This is preclinical work in rats and does not translate directly to clinical liver care.
- Research picture: reviews test multi-point protocols rather than single points, and results for the conditions LV14 is used within are mixed. A Cochrane review found no robust evidence for acupuncture in functional dyspepsia (Lan et al., 2014), meta-analyses of reflux and of cyclic breast pain report possible benefit but rate the underlying trials as low quality (Zhu et al., 2017; Shi et al., 2024), and individual patient data pooling supports modest, durable effects for chronic pain generally (Vickers et al., 2018).
- Practice and de qi: expect a shallow, angled insertion of about 0.5 to 1 cun along the rib space and a sensation of local heaviness, warmth or spreading distention that may travel along the intercostal space toward the sternum or epigastrium. Deep perpendicular insertion is avoided because it carries a substantial pneumothorax risk (Deadman et al., 2009), and pneumothorax remains the most reported serious adverse event in acupuncture safety surveillance despite being rare (Witt et al., 2009).
Tight Ribs, Constant Sighing, and a Chest That Never Fully Relaxes?
Rib-side tension rarely shows up alone. It usually travels with shallow breathing, upper abdominal pressure, and a jaw or neck that has been braced for months. At Morningside Acupuncture we use LV14 as a careful, shallow local point in the sixth rib space, combined with distal points and hands-on work through the intercostals and obliques, to give the chest wall a reason to let go. Schedule a visit and we'll map where your breathing is getting stuck.
Schedule NowAnatomy of LV14: Why the Sixth Intercostal Space Is Such an Important Location
LV14 sits on the front of the chest wall, in the sixth intercostal space, on the vertical line dropped from the nipple and about 4 cun lateral to the midline. From the surface inward, the needle passes skin and subcutaneous fat, then the lower fibers of pectoralis major or, slightly more laterally, a digitation of serratus anterior, then the external and internal intercostal muscles bridging ribs six and seven. In many people the upper attachments of the external oblique and the costal cartilages are only a finger's width below.
This tissue works constantly: every breath, cough, twist, and forward-leaning hour at a desk loads the intercostals, and after a rib strain, a bad cough, or a period of high stress breathing, the space can become locally tender, stiff, and reactive to pressure. Because chest surface landmarks shift with body type and breast tissue, Deadman's Manual of Acupuncture advises counting down from the second rib at the level of the sternal angle rather than eyeballing the position.
The nerve geography is what makes this a useful point rather than just a sore spot. The sixth intercostal nerve runs the space, giving off lateral and anterior cutaneous branches, and its cell bodies sit in mid-thoracic dorsal root ganglia. Visceral afferents from the stomach, the distal esophagus, the gallbladder and the liver capsule travel with the greater splanchnic nerve into roughly the same T5 to T9 segments, and the breast is supplied from the T4 to T6 range.
That shared entry zone is the practical basis for two things clinicians see all the time: upper abdominal or gallbladder irritation referring pain to the lower rib margin, and needling of the trunk changing how the gut feels. Experimental work on somato-autonomic reflexes shows that stimulating the trunk and stimulating the limbs are not equivalent, with trunk segments engaging sympathetic pathways to the stomach while limb points tend to work through vagal routes (Uchida et al., 2017).
Needling here also recruits descending inhibition from brainstem circuitry, which dampens dorsal horn transmission beyond the treated segment (Zhao, 2008). One point-specific study is worth noting with appropriate caution: thermal stimulation over the right Qimen region in rats reduced oxidative and inflammatory markers of liver ischemia and reperfusion injury, and the authors framed the result as a somatovisceral reflex rather than an energetic transfer (Hsieh et al., 2014).
Deep structures set the needling rules. The intercostal neurovascular bundle runs in the costal groove along the lower border of the rib above, so the safer track is angled along the space, closer to the upper border of the lower rib. Deep to the intercostal muscles lie the parietal pleura and lung, with the dome of the liver on the right and the stomach and diaphragm on the left.
For that reason the standard technique is oblique insertion directed medially or laterally, about 0.5 to 1 cun, and Deadman's Manual of Acupuncture is explicit that deep perpendicular or oblique needling here carries a substantial risk of pneumothorax. Prospective safety data suggest serious events are uncommon in trained hands, but pneumothorax is still the serious event most often reported after acupuncture, which is exactly why chest points are needled shallowly and with the anatomy in mind (Witt et al., 2009).
Related Liver Channel Related Intercostal Muscles Trigger PointsLV14 (LR14) at a Glance: Classification, Location, and Clinical Use
| Category | Detail |
|---|---|
| Traditional Name | Qimen (Cycle Gate, also translated Cyclic Gate), LV14 or LIV-14, liver 14 |
| Channel Classification | Fourteenth and final point of the Liver channel (Foot Jueyin), and the closing point of the twelve-channel circulation that begins at LU1 (LV14, also written LIV14 or LR14) |
| Point Categories | Front-mu (gathering) point of the Liver; meeting point of the Liver and Spleen channels with the Yin Linking vessel (Yin Wei mai) |
| Precise Location | On the front of the rib cage in the sixth intercostal space, on the mamillary (nipple) line, 4 cun lateral to the anterior midline; count down from the second rib at the sternal angle to confirm the space |
| Tissue Stimulated | Skin and subcutaneous tissue over the lower fibers of pectoralis major, with the external and internal intercostal muscles in the space itself and the upper abdominal oblique attachments just below the costal margin |
| Needle Depth / Direction | Oblique insertion directed medially or laterally along the rib space, 0.5 to 1 cun; deep perpendicular or oblique insertion is avoided because of substantial pneumothorax risk |
| De Qi Sensation | Local heaviness, warmth, or a spreading ache along the intercostal space, sometimes travelling toward the sternum, the epigastrium, or around the lower rib margin; sharp or breath-catching sensation means the angle should be adjusted |
| Primary Clinical Uses | Rib-side and lower chest pain and distention, premenstrual breast distention and tenderness, reflux, belching and hiccup attributed traditionally to Liver and Stomach disharmony, and the tight chest with frequent sighing and irritability that accompanies sustained stress |
| Common Point Combinations |
|
In the classical literature summarized by Deadman's Manual of Acupuncture, Qimen is presented as the front-mu point of the Liver, the surface site where that organ's qi was traditionally said to collect, and as a crossing point of the Liver and Spleen channels with the Yin Linking vessel. Its attributed actions are to spread Liver qi, invigorate blood and disperse accumulations, and harmonize the Liver with the Stomach.
The classical indication lists cluster into four recognizable groups: chest and rib-side fullness, pain and palpable masses with frequent sighing; upper digestive rebellion such as epigastric distention, acid regurgitation, vomiting and hiccup; gynecological and post-partum presentations, including the famous pattern in which cold penetrates during menstruation or after childbirth and transforms into heat with alternating chills and fever and disordered speech at night; and scattered systemic entries such as jaundice, malaria, and running piglet qi.
Commentators contrast it with LV13 (Zhangmen), which was directed at the middle and lower abdomen, while Qimen was said to act on the middle and upper trunk, and they connect its use for sharp chest pain to its Yin Linking vessel association.
What is striking is that a pre-anatomical tradition assigned a single rib-space point to precisely the cluster of complaints, chest wall, breast, stomach, esophagus and gallbladder, that modern segmental neuroanatomy would later place in the same spinal levels.
Why LV14 Is Used for Reflux, Belching, and Stress-Linked Digestive Symptoms
Patients are often surprised that a point between two ribs is chosen for heartburn, upper abdominal pressure, or belching. The reason is segmental. Sensory nerves from the sixth intercostal space and sensory nerves from the stomach, the lower esophagus, the gallbladder and the liver capsule converge on overlapping mid-thoracic levels of the spinal cord.
That convergence is a two-way street: it explains why an irritated stomach or gallbladder can produce a sore, tender lower rib margin, and it is the basis for stimulating the body wall to influence how the viscera are regulated and how strongly their signals are felt. Reflex studies show that stimulating the chest and abdominal wall engages sympathetic pathways to the gut, while limb points recruit vagal pathways, which is one reason effective protocols usually combine both (Uchida et al., 2017).
There is a second, broader mechanism. Needling activates small-diameter afferents that switch on descending inhibitory systems in the midbrain and brainstem, releasing endogenous opioids, serotonin and noradrenaline at the dorsal horn and reducing the gain on incoming pain signals (Zhao, 2008). For a patient whose ribs feel bruised, whose breathing is shallow, and whose stomach reacts to every stressful email, that combination of segmental modulation and system-wide inhibition matters more than any single local effect.
Mechanistic reviews of acupuncture in functional dyspepsia describe changes in gastric accommodation, autonomic balance and central processing across trials, although the studies vary widely in design and quality (Guo et al., 2020).
The same logic applies to premenstrual breast distention. The breast is innervated from the upper to mid-thoracic segments, the chest wall tissue underneath it is loaded by posture and by the same guarding patterns that follow stress, and classical practice used LV14 as the adjacent point for cyclical breast fullness. A recent meta-analysis of acupuncture for cyclic and noncyclic breast pain found signals of benefit but flagged the small, methodologically limited trial base, so this is best framed as a reasonable adjunct rather than a settled treatment (Shi et al., 2024).
What the Research Shows for LV14 (LR14)
One note on naming before the evidence: in the research literature this point is usually listed as LR14, the WHO standard code, and sometimes as LV14 or LIV14, so it is worth searching all three if you want to read the studies below in full.
Almost no trial tests LV14 by itself. Reviews evaluate whole protocols in which Qimen may be one of six to twelve points, so the honest reading is that the evidence speaks to acupuncture as a package for a given condition, and that LV14 earns its place in that package on anatomical and traditional grounds rather than on point-specific trial data. The gastrointestinal literature in particular is inconsistent, with a Cochrane review finding the evidence insufficient and later meta-analyses reporting benefit in low-quality trials. The table below summarizes what the better sources actually say.
| Study | Type | Focus | Key Finding |
|---|---|---|---|
| Lan et al., 2014 | Cochrane systematic review | Manual acupuncture and electroacupuncture for functional dyspepsia | The reviewers concluded that the available trials were not robust enough to establish effectiveness or safety, so claims about acupuncture for dyspepsia should stay modest. |
| Zhu et al., 2017 | Systematic review and meta-analysis | Acupuncture, alone or added to medication, for gastro-oesophageal reflux disease | Pooled results suggested better symptom improvement when acupuncture was added to standard medication, though the authors cautioned that sample sizes were small and trial quality poor. |
| Shi et al., 2024 | Systematic review and meta-analysis | Acupuncture for cyclic and noncyclic breast pain in women | Across eleven studies the reviewers found possible reductions in breast pain intensity, with the certainty of evidence limited by risk of bias. |
| Guo et al., 2020 | Systematic review of mechanism studies | Physiological effects of acupuncture and electroacupuncture in functional dyspepsia patients | Trials report changes in gastric motility, autonomic measures and central processing, but methodological quality varied and mechanisms remain provisional. |
| Uchida et al., 2017 | Narrative review of reflex physiology | Somatoautonomic reflexes underlying acupuncture and related therapies | Segmental somatic stimulation can alter visceral function through defined reflex pathways, with trunk and limb sites producing different autonomic effects. |
| Hsieh et al., 2014 | Controlled animal study | Thermal stimulation at the right Qimen (LR14) region before hepatic ischemia in rats | Preconditioning reduced liver enzyme and inflammatory markers, which the authors attributed to a somatovisceral reflex; preclinical only, with no direct clinical claim. |
| Vickers et al., 2018 | Individual patient data meta-analysis | Acupuncture across chronic musculoskeletal, headache and osteoarthritis pain | Acupuncture outperformed sham and no-acupuncture controls with effects that persisted over twelve months, supporting its use as one component of pain care. |
| Witt et al., 2009 | Prospective observational safety study | Adverse events across 2.2 million treatments in 229,230 patients | Serious events were rare, with pneumothorax among the few reported, reinforcing why chest points such as LV14 are needled shallowly and obliquely. |
Reflux, Belching, and Bloating That Flare With Stress?
Many patients tell us their heartburn and upper abdominal fullness track their week, not their diet. Qimen sits in the same spinal segments as the stomach and lower esophagus, which is why it's a sensible local addition to a digestive protocol alongside points such as PC6, CV12, and ST36. We coordinate care with your gastroenterologist rather than replacing medical evaluation. Book an appointment and let's look at the pattern together.
Schedule NowLV14 in the Context of Trigger Point Work
The LV 14 ribs location overlaps directly with myofascial territory that dry needling addresses. Trigger points in the intercostals produce sharp, well-localized pain in the involved space that worsens with deep breathing, coughing, or trunk rotation, and trigger points in the abdominal obliques near the costal margin have long been described as capable of producing upper abdominal symptoms such as belching, heartburn sensation and bloating (Simons et al., 1999).
Because LV14 sits at the junction of these regions, a shallow angled needle at Qimen is often doing local myofascial work and segmental work at the same time, which is one reason patients frequently describe an immediate easing of the breath after treatment.
At Morningside Acupuncture we typically treat this region as a unit rather than as an isolated point. That may mean LV14 combined with careful dry needling of the intercostals in the tender spaces, the upper external oblique attachments, and pectoralis major or serratus anterior when the shoulder girdle is contributing, followed by distal points such as LV3, PC6 or GB34 to widen the effect. Needling on the chest wall is always shallow and tangential, never perpendicular and deep, and we screen for cardiac, pulmonary, and gastrointestinal red flags before assuming that rib pain is muscular.
LV14 Rib and Digestive Treatment at NYC's Highest-Rated Acupuncture Clinic
Morningside Acupuncture is the highest-rated acupuncture and dry needling clinic in New York City with over 500 five-star Google reviews, and our licensed acupuncturists needle the chest wall conservatively and anatomically. Treatment plans for rib-side pain, premenstrual breast tenderness, and stress-linked digestive symptoms usually pair local points such as LV14 with distal needling, dry needling of the intercostals and obliques, and simple breathing work you can repeat at home. Schedule your first session and we'll build the plan around your symptoms, not a template.
Schedule NowFrequently Asked Questions
Is LV14 the same point as LR14 or LIV14?
Yes. LV14, LR14, and LIV14 are all codes for the same point, Qimen, point 14 of the Liver channel. LR is the WHO standard abbreviation and the one you will see in most research papers. LV is the form used by many American schools and clinics, and LIV appears in several widely used textbooks. You will also come across it written as Liver 14 or LIV-14. Whichever code is used, the location and the uses are the same.
What does LV14 feel like when needled?
Most people feel a brief pinch at the skin, then a dull heaviness or warm, spreading distention along the rib space. The sensation may travel toward the breastbone, around the lower rib margin, or downward toward the upper abdomen, and some patients notice their breathing drop lower in the chest within a minute or two. Because the needle is angled along the space rather than pushed inward, the feeling should stay superficial and diffuse. A sharp, electric, or breath-catching sensation is not the goal and should be reported immediately so the practitioner can adjust or withdraw.
Why treat a point on the ribs for a stomach or breast problem?
Because they share spinal segments. Sensory nerves from the sixth intercostal space enter the spinal cord at mid-thoracic levels, and so do afferents from the stomach, distal esophagus, gallbladder, liver capsule and breast tissue. That convergence is why upper digestive irritation can refer pain to the lower ribs and why stimulating the body wall in that segment can influence visceral regulation and sensitivity through somato-autonomic reflex pathways (Uchida et al., 2017). Classical texts arrived at the same clinical territory from a different framework, calling LV14 the front-mu point of the Liver and using it for both rib-side distention and acid regurgitation.
Can I press LV14 myself between sessions?
Yes, acupressure at Qimen is safe when it is done gently, and no needle is involved. Find the nipple line, then slide down to the rib space two levels below the nipple, which usually sits just above the lower rib margin on that line. Lay two flat fingerpads into the soft space between the ribs rather than digging into the bone, and press with light to moderate pressure while exhaling slowly for 30 to 60 seconds. Release, breathe normally for a few breaths, and repeat two or three times per side, up to twice a day. Small circular kneading also works well. Keep pressure off breast tissue itself, skip it entirely if you have a recent rib injury, unexplained chest pain, or a skin lesion in the area, and stop if pressing reproduces sharp pain or shortness of breath.
Is LV14 safe to needle?
In trained hands, yes, but it is a point that demands respect. The lung and pleura sit beneath the intercostal muscles, with the liver on the right and the stomach on the left, so the standard technique is oblique insertion along the rib space to a depth of roughly 0.5 to 1 cun. Deadman's Manual of Acupuncture states plainly that deep perpendicular or oblique needling here carries a substantial risk of pneumothorax. Large prospective safety data show that serious events after acupuncture are rare, with pneumothorax the most frequently reported one, which is precisely why depth and angle at chest points are not negotiable (Witt et al., 2009). Tell your practitioner if you are very slender, have emphysema or another lung condition, or have had chest surgery.
Where exactly is LV14 located?
LV14 is on the front of the chest in the sixth intercostal space, on the vertical nipple line, about 4 cun lateral to the anterior midline. The reliable way to find it is to locate the sternal angle, identify the second rib at that level, then count down rib by rib to the sixth space and follow it laterally to the nipple line. In practice this lands just above the lower rib margin in most people, one space above GB24 and roughly in line with the lower border of the pectoral muscle. Note that classical sources also describe a separate point called lower Qimen on the same vertical line at the lower border of the tenth rib, which is a different location entirely.
References
- Deadman, P., Al-Khafaji, M., & Baker, K. (2009). A manual of acupuncture. Journal of Chinese Medicine Publications.
- Kim, H. (2008). Handbook of Oriental medicine (3rd ed.). Harmony & Balance Press.
- Simons, D. G., Travell, J. G., & Simons, L. S. (1999). Travell & Simons' myofascial pain and dysfunction: The trigger point manual, Vol. 1: Upper half of body (2nd ed.). Williams & Wilkins.
- Lan, L., Zeng, F., Liu, G. J., Ying, L., Wu, X., Liu, M., & Liang, F. R. (2014). Acupuncture for functional dyspepsia. Cochrane Database of Systematic Reviews, 2014(10), CD008487. https://doi.org/10.1002/14651858.CD008487.pub2
- Zhu, J., Guo, Y., Liu, S., Su, X., Li, Y., Yang, Y., Hou, L., Wang, G., Zhang, J., Chen, J. D. Z., Wang, Q., Wei, R., & Wei, W. (2017). Acupuncture for the treatment of gastro-oesophageal reflux disease: A systematic review and meta-analysis. Acupuncture in Medicine, 35(5), 316-323. https://doi.org/10.1136/acupmed-2016-011205
- Shi, H., Chen, H., Gao, S., Fang, J., Zhu, L., & Liu, Z. (2024). Acupuncture for cyclic and noncyclic breast pain in women: A systematic review and meta-analysis of randomized controlled trials. European Journal of Integrative Medicine, 68, 102355. https://doi.org/10.1016/j.eujim.2024.102355
- Guo, Y., Wei, W., & Chen, J. D. Z. (2020). Effects and mechanisms of acupuncture and electroacupuncture for functional dyspepsia: A systematic review. World Journal of Gastroenterology, 26(19), 2440-2457. https://doi.org/10.3748/wjg.v26.i19.2440
- Uchida, S., Kagitani, F., & Sato-Suzuki, I. (2017). Somatoautonomic reflexes in acupuncture therapy: A review. Autonomic Neuroscience, 203, 1-8. https://doi.org/10.1016/j.autneu.2016.11.001
- Hsieh, C. C., Hsieh, S. C., Chiu, J. H., & Wu, Y. L. (2014). Preconditioning somatothermal stimulation on Qimen (LR14) reduces hepatic ischemia/reperfusion injury in rats. BMC Complementary and Alternative Medicine, 14, 18. https://doi.org/10.1186/1472-6882-14-18
- Witt, C. M., Pach, D., Brinkhaus, B., Wruck, K., Tag, B., Mank, S., & Willich, S. N. (2009). Safety of acupuncture: Results of a prospective observational study with 229,230 patients and introduction of a medical information and consent form. Forschende Komplementarmedizin, 16(2), 91-97. https://doi.org/10.1159/000209315
- Zhao, Z. Q. (2008). Neural mechanism underlying acupuncture analgesia. Progress in Neurobiology, 85(4), 355-375. https://doi.org/10.1016/j.pneurobio.2008.05.004
- Vickers, A. J., Vertosick, E. A., Lewith, G., MacPherson, H., Foster, N. E., Sherman, K. J., Irnich, D., Witt, C. M., & Linde, K. (2018). Acupuncture for chronic pain: Update of an individual patient data meta-analysis. Journal of Pain, 19(5), 455-474. https://doi.org/10.1016/j.jpain.2017.11.005
Disclaimer: This web site is intended for educational and informational purposes only. Reading this website does not constitute providing medical advice or any professional services. This information should not be used for diagnosing or treating any health issue or disease. Those seeking medical advice should consult with a licensed physician. Seek the advice of a medical doctor or other qualified health professional for any medical condition. If you think you have a medical emergency, call 911 or go to the emergency room. No acupuncturist-patient relationship is created by reading this website or using the information. Morningside Acupuncture PLLC and its employees and contributors do not make any express or implied representations with respect to the information on this site or its use. For any legal interpretation of scope of practice in your state, consult a licensed attorney or regulatory authority.
Read more from our blog



