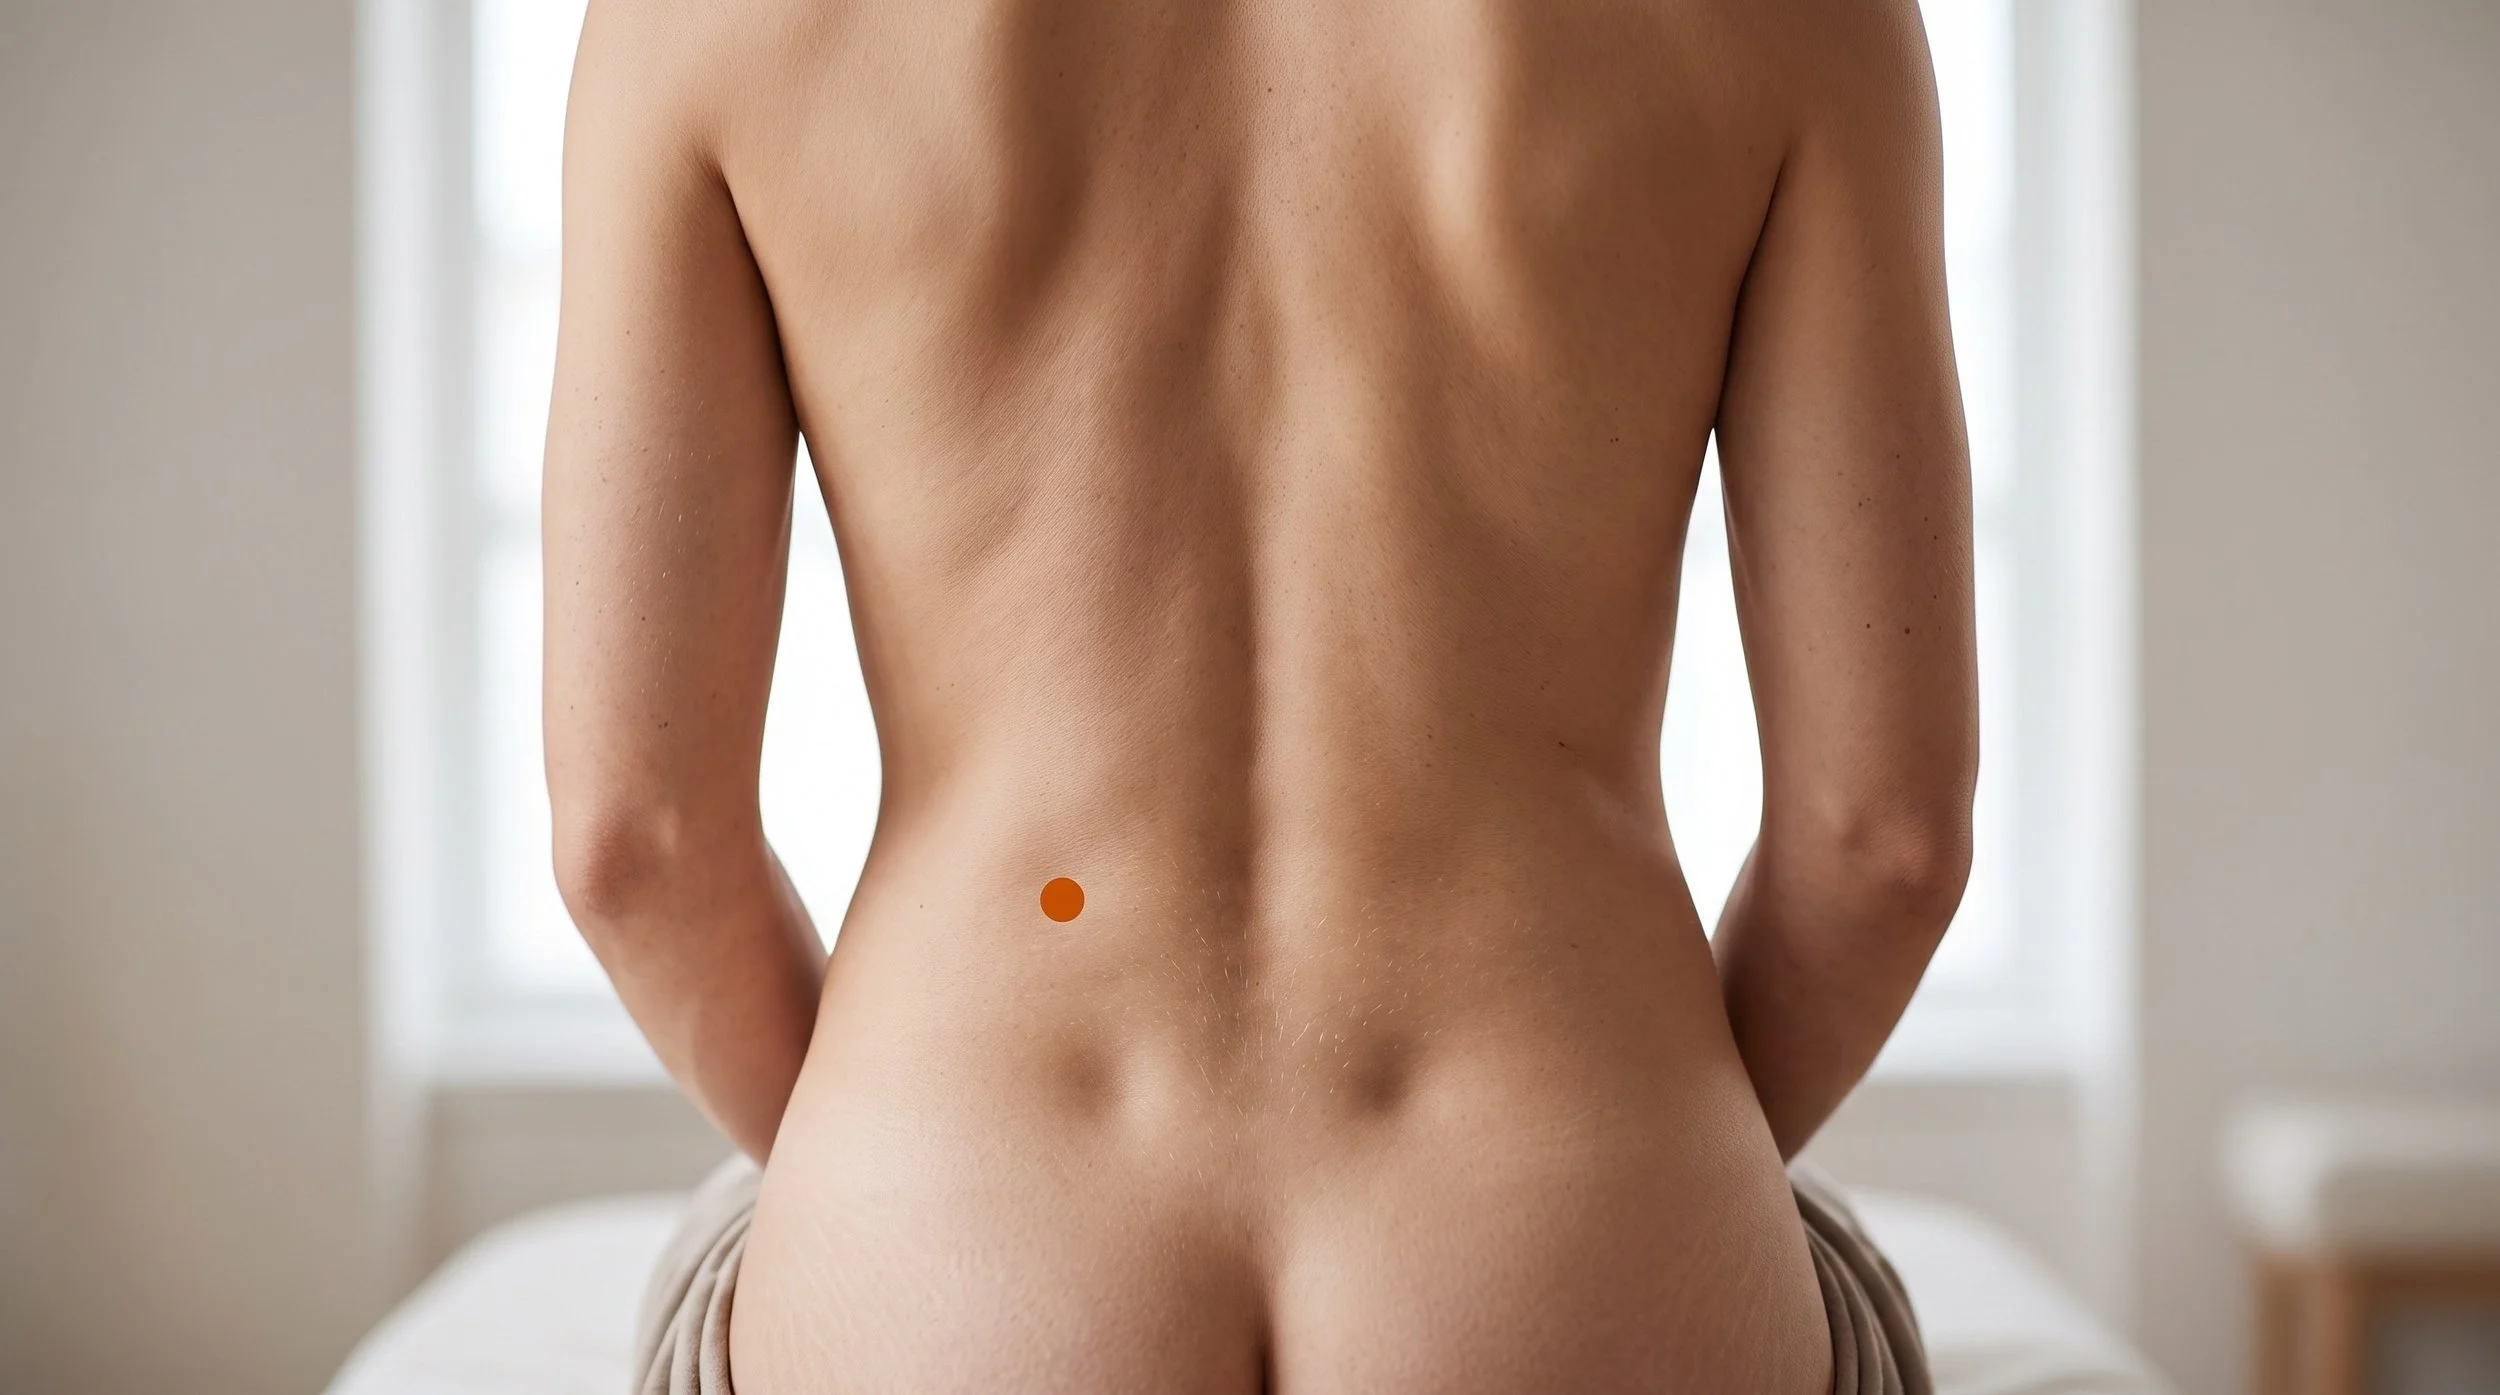
Yaoyan Acupuncture Point (M-BW-24)
The Lumbar Eyes Beside the Spine: Anatomy, Mechanism, and Why This Extra Point Belongs in Almost Every Low Back Treatment
Yaoyan (M-BW-24), translated as Lumbar Eyes, is an extra point rather than a member of any primary channel, and it sits in the two soft hollows that many people can see just lateral to the lumbar spine when they stand relaxed. The classical location is the depression roughly 3.5 cun lateral to the lower border of the fourth lumbar vertebra, level with GV3 (Deadman et al., 2001), which places it over the lateral erector spinae and quadratus lumborum field, close to where the superior cluneal nerves cross the iliac crest.
That anatomy is why the yaoyan acupuncture point earns its place in clinic: it is a direct local access point to the tissue and nerve territory that generates a large share of everyday low back pain, and it has been used exactly that way since it was first recorded in the classical literature.
- Location and layers: yaoyan lies about 3.5 cun lateral to the lower border of L4, level with GV3, in the visible lumbar dimple (Deadman et al., 2001). The needle passes skin and thoracolumbar fascia into the lateral erector spinae and quadratus lumborum region, tissue routinely implicated in mechanical low back pain (Simons et al., 1999).
- Traditional framing: classical sources attribute to M-BW-24 the actions of strengthening the Kidneys and benefiting the lumbar region, with indications centered on Kidney deficiency lumbar aching and low back pain of any origin (Deadman et al., 2001). We read these as descriptions of a chronic, deep, fatigue-linked ache rather than as statements about the kidney organ.
- Nerve story: the lumbar dimple region sits in superior cluneal nerve territory, where lateral branches of the upper lumbar dorsal rami pierce the thoracolumbar fascia near the iliac crest through osteofibrous tunnels that predispose them to mechanical irritation (Kuniya et al., 2013). Suspected cluneal involvement accounts for a meaningful minority of patients presenting with low back and leg symptoms (Kuniya et al., 2014).
- Mechanism: needling here recruits A-delta and C-fiber input into the same lumbar dorsal horn segments that receive the painful tissue's afferents, engaging segmental gating and descending inhibitory pathways that use endogenous opioid, serotonergic and noradrenergic signaling (Zhao, 2008). Local vasodilation and reduced muscle guarding may add to the effect.
- Research picture: pooled patient-level data show acupuncture produces modest but persistent benefits over sham and no-acupuncture controls in chronic musculoskeletal pain (Vickers et al., 2018), and Cochrane work concludes that acupuncture probably reduces pain and improves function in chronic low back pain compared with placebo and usual care (Mu et al., 2020; Rizzo et al., 2025). Trials test whole protocols, not this single point.
- De qi and dosing: patients usually describe a heavy, spreading ache filling the dimple and drifting toward the flank or upper buttock. Classical practice favored moxibustion here for stubborn lumbar pain (Deadman et al., 2001), and moxibustion for chronic low back pain has been reviewed with cautiously favorable but low-certainty results (Chen et al., 2020).
Is Your Low Back Pain Parked Right in Those Dimples?
If your ache lives in the soft hollows beside your spine and worsens with standing, extension, or long days at a desk, that region is exactly what yaoyan targets. At Morningside Acupuncture we palpate the lumbar dimple, the quadratus lumborum, and the cluneal nerve line before choosing needles, then combine local points with distal ones based on what actually reproduces your pain. Treatment often includes electroacupuncture or gentle moxibustion when the pattern is cold, deep, and chronic. Schedule a visit and let us map where your pain is really coming from.
Schedule NowAnatomy of YAOYAN: Why the Lumbar Dimple Is Such an Important Location
Yaoyan sits in a genuine surface landmark, not an abstract one. Standing relaxed, most people show two soft depressions roughly a handbreadth either side of the lumbar spine, just above and medial to the top of the pelvis, and the classical description places the point in that hollow about 3.5 cun lateral to the lower border of L4, level with GV3 (Deadman et al., 2001).
Under the skin and subcutaneous fat the needle meets the posterior layer of the thoracolumbar fascia, then the lateral border of the erector spinae column (iliocostalis lumborum), and deeper still the quadratus lumborum bridging the twelfth rib, the transverse processes, and the iliac crest. This is loaded tissue: it works eccentrically every time you bend, lift, carry a bag on one shoulder, or sit slumped for hours, and it is a classic home for taut bands and referred pain into the buttock and hip (Simons et al., 1999).
The nerve geography is what makes this location more than a convenient muscle target. Lateral branches of the upper lumbar dorsal rami become the superior cluneal nerves, which pierce the thoracolumbar fascia near the posterior iliac crest and travel through narrow osteofibrous tunnels before supplying the skin over the upper buttock; cadaveric dissection has shown these tunnels are common and that the medial branch is the one most often at risk (Kuniya et al., 2013).
Prospective clinical work suggests cluneal nerve disorder explains a notable fraction of patients labeled as having nonspecific low back pain with leg symptoms (Kuniya et al., 2014). Needling into this field delivers strong afferent input to the same upper lumbar spinal segments that receive nociceptive traffic from the fascia, muscle, facet joints, and skin of the region. Because those inputs converge on shared dorsal horn neurons, stimulation can dampen transmission locally while also recruiting brainstem descending inhibition mediated by opioid, serotonergic, and noradrenergic systems (Zhao, 2008).
Deep structures matter for safety, though this is a comparatively forgiving area. At the L4 level the kidneys sit well above the point, and the iliac crest forms a bony floor below and lateral, but beyond the quadratus lumborum lies the retroperitoneal space, so depth and angle still deserve respect in very lean patients. The conventional technique is straightforward perpendicular insertion of 1 to 1.5 cun (Deadman et al., 2001), aiming into muscle rather than steeply medially toward the spinal canal or steeply laterally under the ribs.
Classical practice also favored moxibustion at this point for entrenched lumbar pain, and warming techniques remain a reasonable adjunct when the presentation is chronic, cold-sensitive, and stiff.
Related Acupuncture For Low Back Pain Related Muscles That Cause Low Back PainYAOYAN at a Glance: Classification, Location, and Clinical Use
| Category | Detail |
|---|---|
| Traditional Name | Yaoyan (Lumbar Eyes), M-BW-24 |
| Channel Classification | Extra point of the back and waist region, not on a primary channel; located level with GV3 on the Governing vessel |
| Point Categories | Extraordinary (extra) point only: no five-shu, back-shu, luo, xi-cleft, hui-meeting, or extraordinary vessel intersection designations are assigned to it. The traditional action recorded for M-BW-24 is to strengthen the Kidneys and benefit the lumbar region (Deadman et al., 2001). |
| Precise Location | On the low back, in the depression approximately 3.5 cun lateral to the lower border of the L4 spinous process, level with GV3, in the visible lumbar dimple that sits medial to the upper iliac crest |
| Tissue Stimulated | Thoracolumbar fascia, lateral erector spinae including iliocostalis lumborum, and the quadratus lumborum field, within superior cluneal nerve territory near the iliac crest |
| Needle Depth / Direction | Perpendicular insertion 1 to 1.5 cun into muscle; avoid steep medial angling toward the spinal canal and steep superolateral angling under the twelfth rib. Moxibustion is traditionally applied here. |
| De Qi Sensation | A deep, heavy, filling ache inside the dimple, often spreading laterally toward the flank or downward into the upper buttock; a brief muscle twitch is common when a taut band is engaged |
| Primary Clinical Uses | Acute and chronic low back pain of most causes, quadratus lumborum and lateral erector spinae tenderness, cluneal-region pain over the iliac crest, and the deep fatigue-related lumbar aching described traditionally as Kidney deficiency low back pain |
| Common Point Combinations |
|
Deadman, Al-Khafaji and Baker record that M-BW-24 entered the literature through Song to Keep Up Your Sleeve, and that it has been chosen ever since as a straightforward local point for lumbar pain regardless of cause, whether the episode is acute or has dragged on for years (Deadman et al., 2001). Its traditional action is framed as strengthening the Kidneys and benefiting the lumbar region, and its listed indications are unusually narrow for a classical point: low back pain, Kidney deficiency lumbar pain, and depletion of the body's reserves.
The single classical formula attached to it is not a point combination at all but a dose of moxibustion, seven cones applied directly to the point. What is striking is the plainness of the whole entry. Where many classical points accumulate long and eclectic indication lists, yaoyan stayed anchored to one anatomical problem in one anatomical place, which is roughly how a modern clinician trained in palpation would describe a reliable local treatment site.
Why YAOYAN Is Used for Buttock and Thigh Pain That Looks Like Sciatica
Patients often arrive convinced their pain is a disc, because it starts in the low back and spreads into the buttock and outer thigh. Sometimes it is. But the tissue directly beneath yaoyan can produce a very similar map: the quadratus lumborum and lateral erector spinae refer pain toward the crest, the buttock, and the greater trochanter (Simons et al., 1999), and the superior cluneal nerves supply skin over the upper buttock after threading through tight fascial tunnels at the iliac crest (Kuniya et al., 2013).
When cluneal irritation is the driver, tenderness is reproducible over a small spot on the crest and symptoms may be aggravated by extension, which is a very different exam picture from a true radiculopathy. This pattern is common enough that it accounts for a meaningful share of cases otherwise filed as nonspecific low back pain with leg symptoms (Kuniya et al., 2014).
The mechanism that makes needling useful here is convergence. Skin, fascia, muscle, joint capsule, and nerve trunks from the same spinal levels feed into overlapping populations of dorsal horn neurons, so a needle in the lumbar dimple delivers a strong, well-localized afferent barrage into the exact segments that are already sensitized. That input can reduce transmission at the segmental level and simultaneously trigger descending inhibition from the periaqueductal gray and rostral ventromedial medulla, using endogenous opioids, serotonin, and noradrenaline (Zhao, 2008). Practically, this is why relief often extends beyond the needle site into the referral zone rather than staying under the skin.
There is also a mechanical layer. Needling a taut band frequently produces a visible local twitch and is followed by reduced tenderness and improved pressure pain thresholds, and pooled trial data support dry needling of myofascial trigger points as a short-term option for low back pain, with the usual caveats about heterogeneous protocols and small samples (Liu et al., 2018).
Combined with the general finding that acupuncture protocols probably reduce pain and improve function in chronic low back pain (Mu et al., 2020; Rizzo et al., 2025), yaoyan is best understood as a well-placed access point within a broader plan, not as a stand-alone fix.
What the Research Shows for YAOYAN
No clinical trial has isolated yaoyan on its own, and it would be misleading to suggest otherwise. What the literature tests is multi-point acupuncture protocols for low back pain, and lumbar local points in this region are standard members of those prescriptions. The reasonable reading is that the evidence supports the approach yaoyan belongs to, that effects are real but moderate, and that the point's specific contribution is inferred from anatomy and palpation findings rather than proven by trial data. Certainty across this literature is generally low to moderate, and sham comparisons in acupuncture research are notoriously imperfect.
| Study | Type | Focus | Key Finding |
|---|---|---|---|
| Mu et al., 2020 | Cochrane systematic review (33 trials, 8,270 participants) | Acupuncture for chronic nonspecific low back pain versus sham, no treatment, and usual care | Acupuncture may reduce pain and improve function, with clinically relevant pain benefit chiefly against no treatment and low to moderate certainty overall. |
| Rizzo et al., 2025 | Cochrane overview of 31 reviews (644 trials, 97,183 adults) | Non-pharmacological and non-surgical treatments for low back pain | For chronic low back pain, acupuncture probably reduces pain and improves function compared with placebo and with no treatment or usual care. |
| Vickers et al., 2018 | Individual patient data meta-analysis (about 21,000 patients) | Acupuncture for chronic musculoskeletal pain including back and neck pain | Acupuncture outperformed both sham and no-acupuncture controls, with benefits that persisted over roughly twelve months. |
| Liu et al., 2018 | Systematic review and meta-analysis | Dry needling of myofascial trigger points associated with low back pain | Dry needling appeared to reduce pain and disability in the short term, though the evidence base was small and heterogeneous. |
| Chen et al., 2020 | Systematic review and meta-analysis (10 RCTs, 987 patients) | Moxibustion for chronic low back pain | Moxibustion showed favorable effects on pain scores in several comparisons, but the authors judged the evidence low quality and the conclusions inconclusive. |
| Kuniya et al., 2014 | Prospective clinical study | Superior cluneal nerve disorder as a source of low back pain and leg symptoms | A clinically relevant proportion of patients with low back and leg symptoms showed findings consistent with superior cluneal nerve involvement near the iliac crest. |
| Zhao, 2008 | Narrative review of mechanism research | Neural mechanisms of acupuncture analgesia | Needle stimulation engages segmental spinal inhibition and descending opioid, serotonergic, and noradrenergic pathways. |
Sciatica-Like Pain That Imaging Cannot Explain?
Pain that spreads from the low back into the buttock and outer thigh is not always a disc, and the superior cluneal nerves crossing the iliac crest are an underrecognized source (Kuniya et al., 2013). Yaoyan sits in that territory, which makes it a practical needling site when tenderness is reproducible over the crest. We combine it with dry needling of the gluteal and lumbar muscles and with movement retraining so the relief holds. Book an evaluation and we will test the region carefully before treating it.
Schedule NowYAOYAN in the Context of Trigger Point Work
Acupuncture, in our definition, means treatment with an acupuncture needle, and dry needling is one of the hundreds of styles that fit inside that definition. Yaoyan is a useful illustration, because the classical coordinates and a modern myofascial target land in nearly the same place. Needling the lumbar dimple engages the lateral erector spinae and the quadratus lumborum, two muscles whose taut bands refer pain into the crest, buttock, and hip in patterns that patients frequently mistake for joint or disc problems (Simons et al., 1999).
When we palpate a band there and the needle reproduces the patient's familiar ache, we are treating the same tissue a Song dynasty practitioner was treating, with better anatomical language for it.
In a typical session at Morningside we use yaoyan as an anchor and build outward: dry needling of the quadratus lumborum and iliocostalis lumborum on the involved side, gluteus medius and gluteus maximus when referral extends into the buttock, and psoas or hip flexor work when extension is limited. Electroacupuncture across two lumbar sites can be added for chronic cases, and moxibustion or cupping when the region feels cold, stiff, and slow to warm up.
Needle depth stays within the conventional 1 to 1.5 cun range, angled into muscle rather than toward the midline, and treatment is always paired with loading and movement advice so the tissue tolerates more than it did before.
YAOYAN Low Back Pain Treatment at NYC's Highest-Rated Acupuncture Clinic
Morningside Acupuncture is the highest-rated acupuncture and dry needling clinic in New York City with over 500 five-star Google reviews, and low back pain is the complaint we treat most often. Our licensed acupuncturists blend classical point selection, including the yaoyan low back point, with trigger point dry needling, electroacupuncture, and cupping in a single evidence-informed session. Whether your pain is three days old or three years old, we build a plan around your exam findings rather than a template. Schedule your appointment today.
Schedule NowFrequently Asked Questions
What does YAOYAN feel like when needled?
Most people feel a dull, heavy, expanding ache that seems to fill the dimple from the inside, sometimes with a brief cramp-like grab if the needle contacts a taut band. That sensation, called de qi, usually settles within seconds and often gives way to a warm, loosened feeling across the low back. Some patients notice the ache travel toward the flank or upper buttock, which typically means the needle has engaged the referral pattern that has been driving their symptoms. Sharp, electric, or shooting sensations are not expected, and you should tell your acupuncturist immediately if you feel one.
Why needle right where it hurts instead of using distal points?
Both approaches have a role, and good treatment usually uses them together. Local needling at yaoyan puts strong afferent input into the exact spinal segments receiving pain signals from the fascia, muscle, and cluneal nerves of that region, which supports segmental inhibition and mechanically influences the taut tissue itself (Zhao, 2008; Simons et al., 1999). Distal points such as BL40 or LI4 recruit broader descending modulation and are helpful when the low back is too irritable to needle directly. Classically, yaoyan was valued precisely because it is a local point for lumbar pain of any origin (Deadman et al., 2001).
Can I press YAOYAN myself between sessions?
Yes, and it is one of the easier points to self-treat because you can find the dimples with your thumbs. Stand or sit upright, slide your thumbs about a handbreadth out from the spine at belt height, and settle into the soft hollows just above the top rim of your pelvis. Press with steady, moderate pressure that feels like a satisfying ache rather than a sharp pain, hold for 30 to 60 seconds, release, and repeat three to five times per side, once or twice daily. Small circular pressure or leaning back into a tennis ball against a wall works well too. A heating pad over the same area for 10 to 15 minutes echoes the classical use of moxibustion here. Stop if pressure creates numbness, tingling, or radiating leg symptoms, and check in with a clinician instead.
Is YAOYAN safe to needle?
In trained hands, yes. The standard technique is perpendicular insertion of 1 to 1.5 cun into muscle (Deadman et al., 2001), and at the L4 level the kidneys sit well above the point while the iliac crest provides a bony boundary below and lateral. The main cautions are avoiding steep medial angling toward the spinal canal, avoiding steep superolateral angling up under the twelfth rib, and adjusting depth in very lean patients. Minor bruising or a day of local soreness is the most common side effect. Tell your acupuncturist if you take blood thinners, are pregnant, or have had lumbar surgery or hardware placed, since those all change technique.
Where exactly is YAOYAN located?
Find the crest of your pelvis at the sides and follow it toward your spine. Yaoyan sits in the depression roughly 3.5 cun lateral to the lower border of the L4 spinous process, level with GV3 (Deadman et al., 2001), which in most people corresponds to the visible dimple about one handbreadth out from the midline, just above and medial to the crest. It is a bilateral point, so there is one on each side. If you relax the low back while standing, the hollows are often easy to see, and the tender one is usually the side that needs attention.
References
- Deadman, P., Al-Khafaji, M., & Baker, K. (2009). A manual of acupuncture. Journal of Chinese Medicine Publications.
- Simons, D. G., Travell, J. G., & Simons, L. S. (1999). Travell & Simons' myofascial pain and dysfunction: The trigger point manual, Vol. 1: Upper half of body (2nd ed.). Williams & Wilkins.
- Mu, J., Furlan, A. D., Lam, W. Y., Hsu, M. Y., Ning, Z., & Lao, L. (2020). Acupuncture for chronic nonspecific low back pain. Cochrane Database of Systematic Reviews, 12(12), CD013814. https://doi.org/10.1002/14651858.CD013814
- Rizzo, R. R. N., Cashin, A. G., Wand, B. M., Ferraro, M. C., Sharma, S., Lee, H., O'Hagan, E., Maher, C. G., Furlan, A. D., van Tulder, M. W., & McAuley, J. H. (2025). Non-pharmacological and non-surgical treatments for low back pain in adults: An overview of Cochrane reviews. Cochrane Database of Systematic Reviews, 2025(3), CD014691. https://doi.org/10.1002/14651858.CD014691.pub2
- Vickers, A. J., Vertosick, E. A., Lewith, G., MacPherson, H., Foster, N. E., Sherman, K. J., Irnich, D., Witt, C. M., & Linde, K. (2018). Acupuncture for chronic pain: Update of an individual patient data meta-analysis. Journal of Pain, 19(5), 455-474. https://doi.org/10.1016/j.jpain.2017.11.005
- Zhao, Z. Q. (2008). Neural mechanism underlying acupuncture analgesia. Progress in Neurobiology, 85(4), 355-375. https://doi.org/10.1016/j.pneurobio.2008.05.004
- Kuniya, H., Aota, Y., Saito, T., Kamiya, Y., Funakoshi, K., Terayama, H., & Itoh, M. (2013). Anatomical study of superior cluneal nerve entrapment. Journal of Neurosurgery: Spine, 19(1), 76-80. https://doi.org/10.3171/2013.4.SPINE12683
- Kuniya, H., Aota, Y., Kawai, T., Kaneko, K., Konno, T., & Saito, T. (2014). Prospective study of superior cluneal nerve disorder as a potential cause of low back pain and leg symptoms. Journal of Orthopaedic Surgery and Research, 9, 139. https://doi.org/10.1186/s13018-014-0139-7
- Liu, L., Huang, Q. M., Liu, Q. G., Thitham, N., Li, L. H., Ma, Y. T., & Zhao, J. M. (2018). Evidence for dry needling in the management of myofascial trigger points associated with low back pain: A systematic review and meta-analysis. Archives of Physical Medicine and Rehabilitation, 99(1), 144-152.e2. https://doi.org/10.1016/j.apmr.2017.06.008
- Chen, F. Q., Ge, J. F., Leng, Y. F., Li, C., Chen, B., & Sun, Z. L. (2020). Efficacy and safety of moxibustion for chronic low back pain: A systematic review and meta-analysis of randomized controlled trials. Complementary Therapies in Clinical Practice, 39, 101130. https://doi.org/10.1016/j.ctcp.2020.101130
Disclaimer: This web site is intended for educational and informational purposes only. Reading this website does not constitute providing medical advice or any professional services. This information should not be used for diagnosing or treating any health issue or disease. Those seeking medical advice should consult with a licensed physician. Seek the advice of a medical doctor or other qualified health professional for any medical condition. If you think you have a medical emergency, call 911 or go to the emergency room. No acupuncturist-patient relationship is created by reading this website or using the information. Morningside Acupuncture PLLC and its employees and contributors do not make any express or implied representations with respect to the information on this site or its use. For any legal interpretation of scope of practice in your state, consult a licensed attorney or regulatory authority.
Read more from our blog



