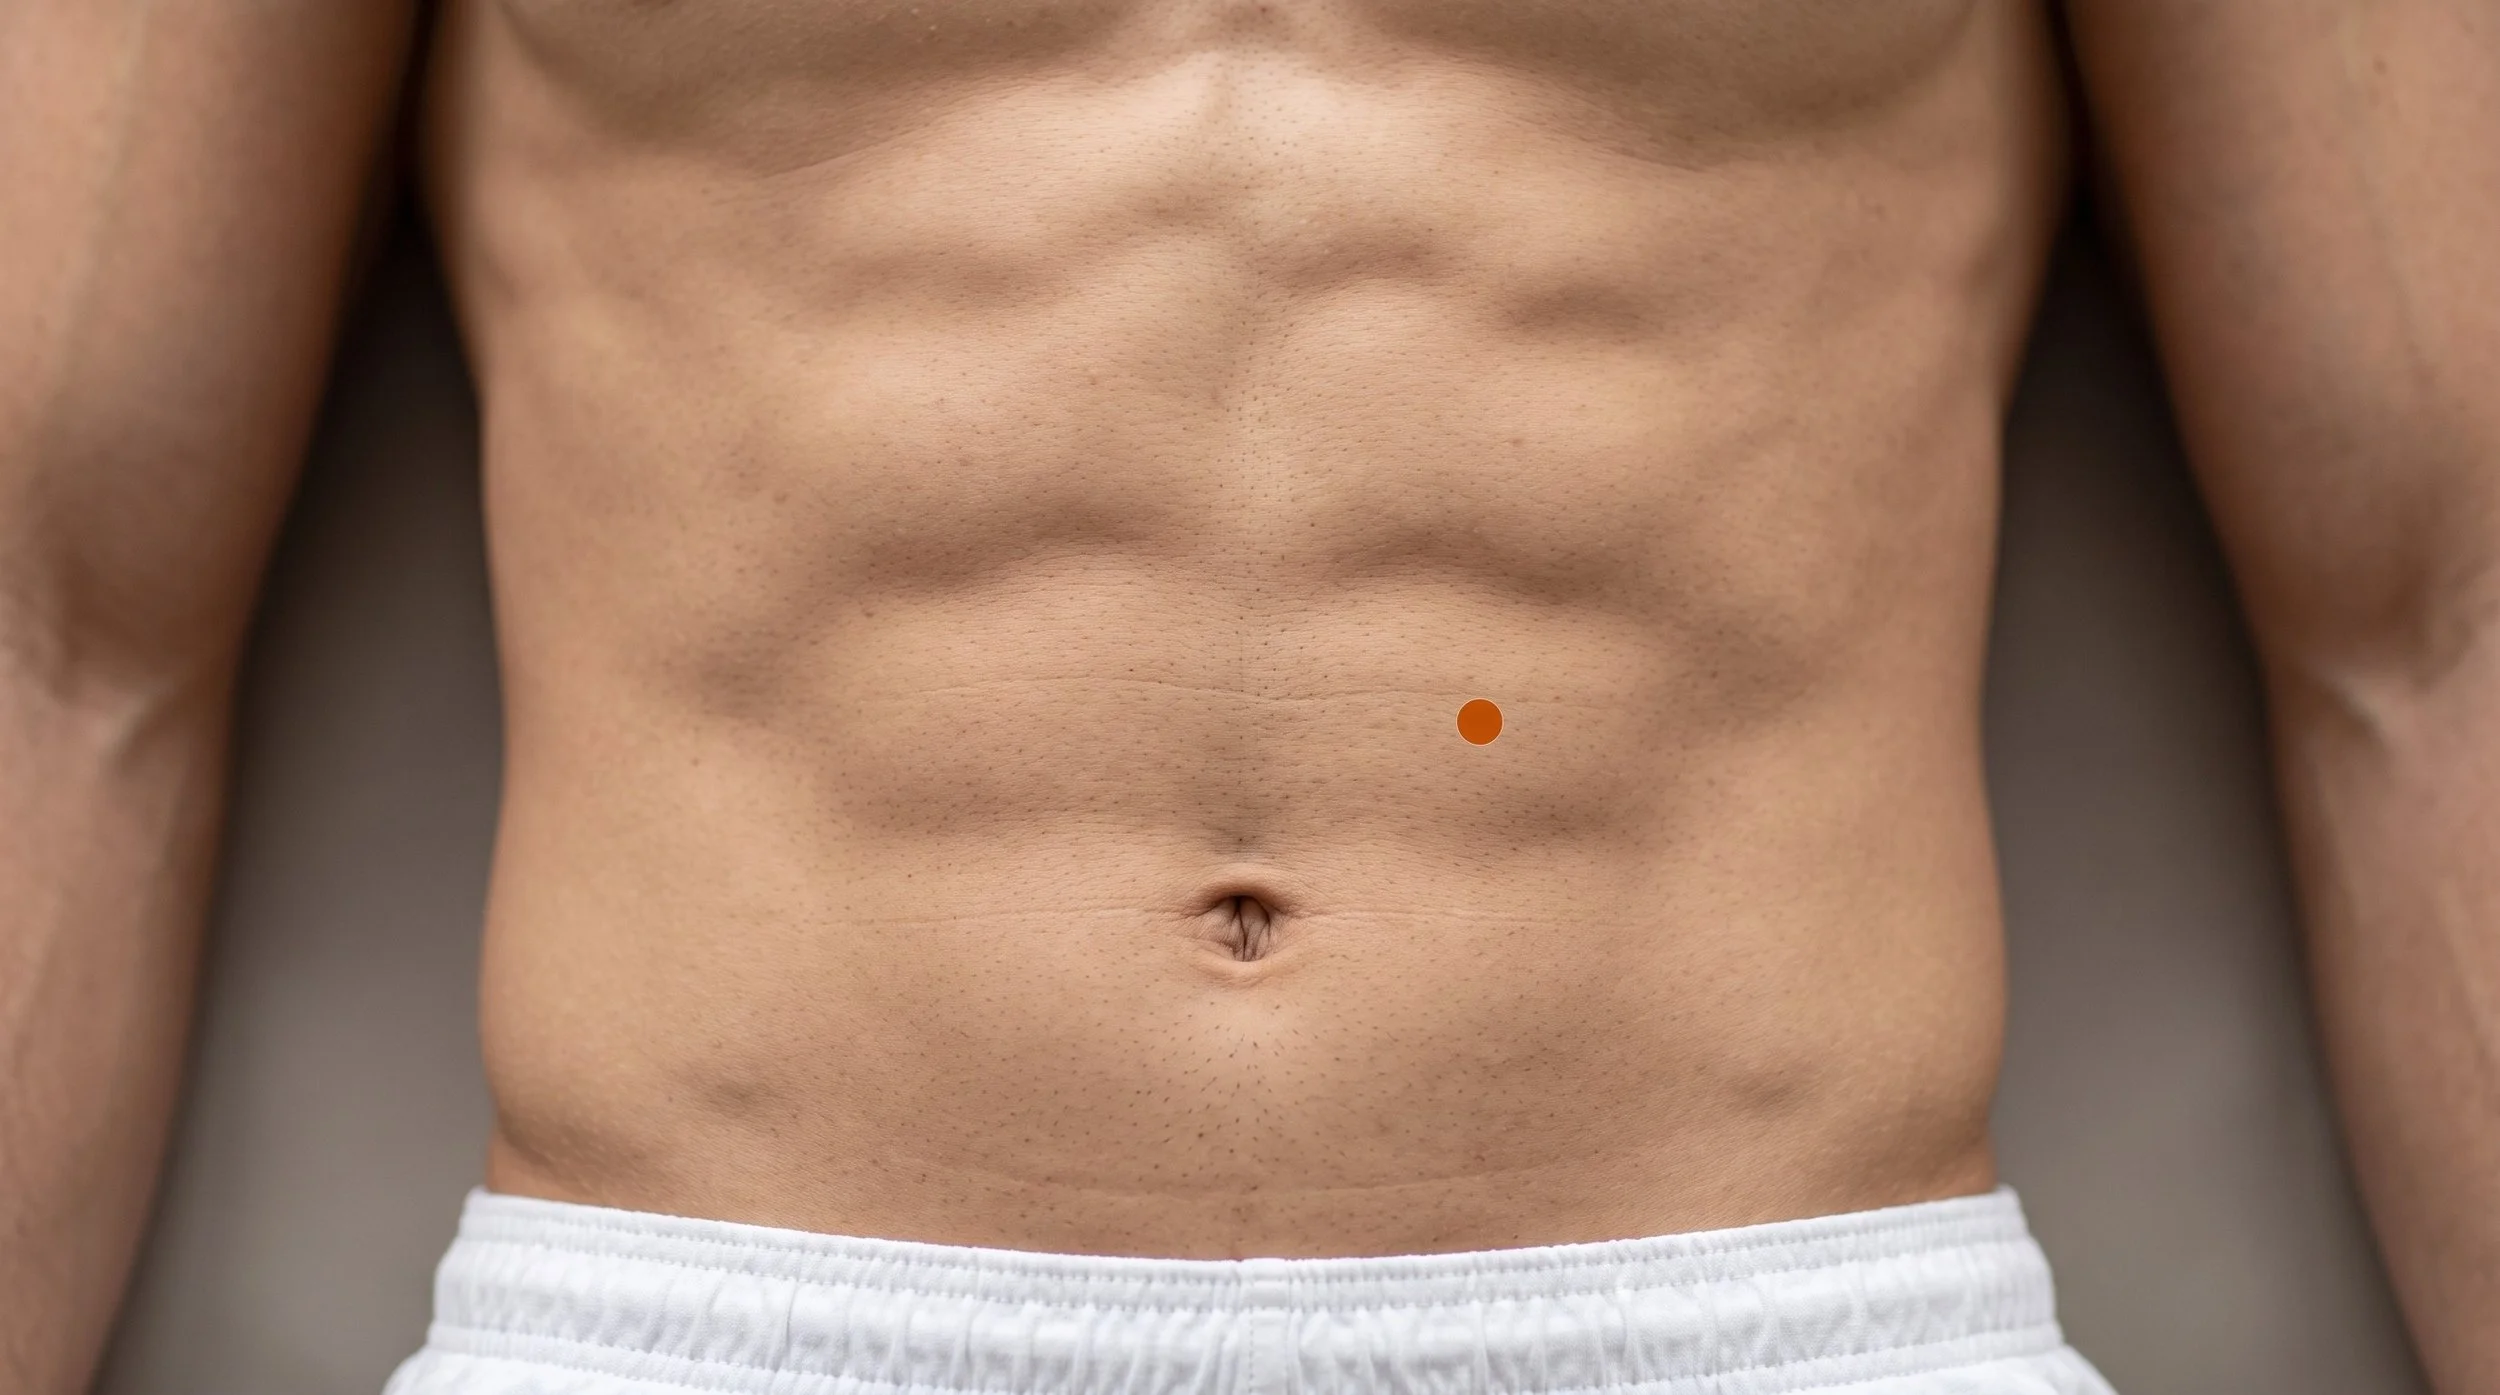
ST23 Acupuncture Point (Taiyi)
Supreme Unity Above the Navel: Anatomy, Segmental Gut Reflexes, and Why This Mid Abdominal Stomach Point Bridges Digestion and Distress
ST23, known as Taiyi (Supreme Unity), sits on the belly two cun above the navel and two cun out from the midline, right in the meat of the rectus abdominis and level with CV10. In plain terms, if you find the halfway mark between your belly button and the lower tip of your breastbone, then slide sideways about two finger widths short of the outer edge of the six-pack muscle, you are on it.
The st23 acupuncture point matters clinically because it sits directly over the segmental territory that serves the stomach, small intestine, and transverse colon, and because the classical literature assigned it an unusual double job: settling the digestive middle and settling the mind. That pairing is exactly what many patients bring through the door, a queasy, cramping, appetite-poor abdomen that gets worse when life gets loud.
- Location and layers: ST23 lies 2 cun above the umbilicus and 2 cun lateral to the midline, level with CV10, with the needle passing skin, subcutaneous fat, the anterior rectus sheath, and rectus abdominis before reaching deeper fascia (Deadman et al., 2007).
- Traditional attributions: classical sources credit Taiyi with harmonising the middle burner and calming the spirit, and list epigastric and abdominal pain, poor appetite, diarrhoea, and agitated mental states among its indications (Deadman et al., 2007; Shanghai College of Traditional Chinese Medicine, 1981).
- Mechanism in modern terms: the point sits in roughly T9 to T10 territory, where anterior cutaneous branches of the intercostal nerves and gut visceral afferents converge on shared dorsal horn neurons, the anatomical basis for somatovisceral and viscerosomatic effects (Uchida et al., 2017).
- Directionality matters: animal work suggests abdominal stimulation tends to recruit spinal sympathetic reflexes that damp gastric activity, while limb points more readily drive vagal facilitation, which is one reason abdomen plus leg combinations are standard (Uchida et al., 2017; Guo et al., 2020).
- Research picture: reviews of acupuncture for functional dyspepsia and irritable bowel syndrome report symptom and quality of life improvements with generally low certainty evidence and heterogeneous protocols, so ST23 should be understood as one component of a formula rather than a tested stand-alone (Pang et al., 2016; Manheimer et al., 2012).
- De qi at ST23 is usually a dull, heavy, spreading fullness under the needle rather than a sharp sensation, and patients often notice gut gurgling or a slow softening of the abdominal wall within a few minutes (Deadman et al., 2007).
Is Your Stomach Reacting to Your Stress Levels?
If your digestion tightens up the moment your week gets busy, treatment that only targets the gut tends to miss half the picture. At Morningside Acupuncture we use ST23 alongside distal points and breath-paced abdominal palpation to address both the belly wall and the autonomic tone driving it. Our licensed acupuncturists build a plan around your specific pattern of pain, appetite, and bowel changes. Schedule a visit and let's map what is actually setting your symptoms off.
Schedule NowAnatomy of ST23: Why the Mid Abdominal Rectus Sheath Is Such an Important Location
From the surface down, a needle at ST23 passes through skin, a variable layer of subcutaneous fat, the anterior leaf of the rectus sheath, and then the rectus abdominis itself. This part of the abdominal wall is under constant mechanical load: it braces during coughing, lifting, and sitting up, it shortens in habitual flexed postures, and it tenses reflexively when the gut underneath is irritated.
Because the point lies on the 2 cun line, roughly halfway between the midline and the palpable outer border of the rectus, it usually falls over muscle belly rather than over the linea alba or the lateral edge, which is why practitioners palpate the muscle border first rather than measuring blind (Deadman et al., 2007).
The nerve geography is the interesting part. The skin and muscle here are supplied by anterior cutaneous and muscular branches of the lower intercostal nerves, placing ST23 in roughly the T9 to T10 segment. Visceral afferents from the stomach, duodenum, and small intestine funnel into overlapping spinal levels, so somatic input from the abdominal wall and visceral input from the gut arrive at many of the same dorsal horn neurons.
That convergence is the accepted explanation for two clinical observations: gut irritation can produce genuine abdominal wall tenderness, and needling the wall can reflexively alter visceral tone through spinal and supraspinal autonomic pathways (Uchida et al., 2017). Needle stimulation also recruits A-delta and C fiber activity that engages descending inhibitory control from the midbrain and brainstem, the same system implicated in acupuncture analgesia more broadly (Zhao, 2008).
Deeper structures set the safety limits. Within the rectus sheath run the superior epigastric vessels, and beneath the posterior sheath and transversalis fascia lie the peritoneum, transverse colon, and loops of small intestine. Standard practice is perpendicular insertion of about 1 to 1.5 cun, with an explicit caution that in thin patients deep needling can enter the peritoneal cavity (Deadman et al., 2007).
Practically, that means depth is judged by body habitus rather than by a fixed number, the needle is angled and advanced slowly, and the point is skipped or needled very superficially over hernias, recent surgical sites, or a distended abdomen.
Related Stomach Channel Related Rectus Abdominis Trigger PointsST23 at a Glance: Classification, Location, and Clinical Use
| Category | Detail |
|---|---|
| Traditional Name | Taiyi (Supreme Unity), also translated as Great Oneness or Great Yi |
| Channel Classification | Stomach channel of Foot Yangming, abdominal segment |
| Point Categories | No five-shu, meeting, or extraordinary vessel designation is recorded in the sources used here. It is classified as a regular Stomach channel point of the mid abdomen, level with CV10, with traditional actions listed as transforming phlegm and calming the spirit and harmonising the middle jiao (Deadman et al., 2007). |
| Precise Location | On the abdomen, 2 cun above the umbilicus and 2 cun lateral to the anterior midline, level with CV10. The 2 cun line falls midway between the midline and the palpable lateral border of the rectus abdominis. |
| Tissue Stimulated | Skin, subcutaneous fat, anterior rectus sheath, and rectus abdominis; adjacent myofascial targets include the abdominal obliques and transverse abdominis |
| Needle Depth / Direction | Perpendicular, 1 to 1.5 cun, depth scaled to body habitus. Deep insertion can reach the peritoneal cavity in thin patients, so shallower technique is used when the abdominal wall is lean or distended. |
| De Qi Sensation | Dull, heavy, spreading fullness or pressure under the needle, sometimes with warmth or audible gut sounds; sharp or radiating pain means the needle should be adjusted |
| Primary Clinical Uses | Epigastric and abdominal pain, poor appetite, loose stools and abdominal distension, abdominal wall tenderness, and, in classical framing, digestive complaints accompanied by restlessness or agitation |
| Common Point Combinations |
|
Deadman, Al-Khafaji and Baker's A Manual of Acupuncture presents Taiyi as a point with two traditional actions, transforming phlegm to calm the spirit and harmonising the middle burner, and the commentary explains why a belly point was ever given psycho-emotional duties.
The reasoning offered is threefold in traditional terms: several Stomach channel points were held to assist the Spleen in resolving phlegm, the Stomach divergent channel was described as connecting internally to the Heart, and the Stomach channel meets the Governing vessel at points on the face and forehead that were considered to act on the brain and spirit.
Within that framework, phlegm or phlegm-heat generated by a disordered Stomach and Spleen was thought to rise and cloud the Heart, producing agitation, erratic behaviour, and the odd, specific sign of repetitive tongue thrusting that appears in several classical formulas alongside ST23. The name itself points to a Daoist idea of undifferentiated oneness before yin and yang separated, and one explanation connects it to the region of the abdomen where the pure and turbid parts of digestion have not yet been sorted.
What makes the classical pattern striking is not the metaphysics but the clinical observation embedded in it: the old texts kept describing patients whose gut symptoms and emotional turbulence arrived as one complaint, which is precisely the presentation modern gastroenterology now studies under the heading of disorders of gut-brain interaction.
Why ST23 Is Used for Digestive Complaints That Flare With Stress and Anxiety
The first half of the answer is segmental. ST23 sits in roughly the T9 to T10 band of the abdominal wall, and the same spinal segments receive afferent traffic from the stomach, duodenum, and small intestine. When two streams of sensory input converge on shared spinal neurons, influence runs in both directions: an irritated gut can make the overlying abdominal wall genuinely tender and guarded, and needling that wall can feed back into the reflex circuitry that regulates visceral tone.
This is the somatovisceral reflex, and it has been mapped in detail in animal preparations where abdominal stimulation and limb stimulation produce different, and sometimes opposite, effects on gastric activity (Uchida et al., 2017).
The second half is about the descending systems. Needle stimulation activates small-diameter afferents that engage brainstem and midbrain circuits releasing endogenous opioids, serotonin, and noradrenaline onto the spinal cord, dampening the onward transmission of pain signals (Zhao, 2008).
In digestive complaints that involve heightened visceral sensitivity rather than structural disease, that dampening is plausibly part of why patients report less cramping and less urgency, and reviews of acupuncture in functional dyspepsia have specifically examined gastric accommodation, motility, and central processing as candidate mechanisms (Guo et al., 2020). None of this is proof that ST23 in isolation does any of it, but it explains why an abdominal point in this segment is a reasonable choice.
The stress overlay matters clinically. Patients with functional digestive disorders carry higher rates of anxiety and low mood, and a meta-analysis of trials in functional dyspepsia found that acupuncture protocols were associated with improvements in anxiety and depression scores, though the certainty of that evidence was rated very low (Xu et al., 2024). Broader reviews of acupuncture for anxiety report modest benefit with similar methodological limits (Yang et al., 2021).
We use ST23 in these presentations because the point sits at the intersection the patient is actually describing, a gut that reacts to mood and a mood that reacts to the gut, not because needling it resolves anxiety on its own.
What the Research Shows for ST23
A word of calibration before the table. Almost no clinical trial tests ST23 by itself. Reviews evaluate multi-point protocols for conditions like functional dyspepsia and irritable bowel syndrome, where ST23 may or may not appear among six to twelve needles alongside CV12, ST25, ST36, PC6, and others. What the literature can tell us is whether the overall approach shows signal, how confident we can be in that signal, and what mechanisms are biologically plausible. What it cannot tell us is how much of any effect belongs to this particular point.
The honest summary is that the evidence for acupuncture in functional gut disorders is mixed, mostly of low to moderate certainty, and best interpreted as supporting acupuncture as an adjunct rather than a replacement for standard care.
| Study | Type | Focus | Key Finding |
|---|---|---|---|
| Manheimer et al., 2012 | Cochrane systematic review | Acupuncture for irritable bowel syndrome | Acupuncture did not outperform sham in the pooled trials, though it showed benefit compared with some active and no-treatment controls, so the reviewers were cautious about specific point effects. |
| Pang et al., 2016 | Systematic review and meta-analysis | Acupuncture for functional dyspepsia | Pooled results favoured acupuncture for dyspepsia symptom scores and quality of life, but most included trials were rated low quality, which limits confidence. |
| Guo et al., 2020 | Systematic review of mechanisms | Acupuncture and electroacupuncture effects and mechanisms in functional dyspepsia | The review describes candidate mechanisms including gastric motility and accommodation changes and autonomic modulation, while noting substantial heterogeneity across studies. |
| Xu et al., 2024 | Systematic review and meta-analysis | Anxiety and depression outcomes in functional dyspepsia | Acupuncture was associated with improvement in anxiety and depression scores compared with placebo, with the authors grading the evidence as very low quality. |
| Yang et al., 2021 | Systematic review and meta-analysis | Acupuncture for anxiety disorder | A small to moderate pooled effect favoured acupuncture over control conditions, with methodological limitations across the included trials. |
| Uchida et al., 2017 | Physiological review | Somatoautonomic reflexes evoked by acupuncture-like stimulation | Reflex effects on visceral organs vary by the body region stimulated, with abdominal and limb stimulation engaging different autonomic pathways in animal models. |
| Vickers et al., 2018 | Individual patient data meta-analysis | Acupuncture for chronic pain | Acupuncture outperformed both sham and no-acupuncture controls for chronic pain conditions, supporting effects beyond expectation alone while leaving point specificity unresolved. |
Epigastric Pain, Bloating, and Poor Appetite That Keep Coming Back?
Persistent upper abdominal discomfort deserves a careful workup and a treatment plan that respects what your gastroenterologist has already found. Once serious causes are ruled out, ST23 is one of the abdominal points we use to influence the T9 to T10 segment that serves the stomach and small intestine. We combine it with ST36, CV10, and hands-on abdominal work, then track your response session by session. Book an evaluation and we will tell you honestly whether acupuncture is a reasonable fit.
Schedule NowST23 in the Context of Trigger Point Work
ST23 sits squarely in rectus abdominis, a muscle with a well documented habit of producing pain that patients and clinicians both mistake for a gut problem. Trigger points in the upper and mid rectus have been described as referring pain horizontally across the back and as contributing to nausea, bloating, and a sense of abdominal fullness, which is exactly the symptom picture that sends people for imaging (Simons et al., 1999).
When abdominal wall involvement is present, the tenderness typically increases when the patient tenses the muscle by lifting the head off the table, a simple bedside distinction from tenderness that eases with muscle contraction. We check that before deciding how to needle the area.
In practice this means the st 23 abdomen location often gets treated twice over in the same session, once as a classical point with a modest, retained needle and once as a myofascial target if palpation finds a taut band. Dry needling is acupuncture performed with an acupuncture needle under a different reasoning framework, so the technique is the same tool with a different rationale, and at Morningside we are explicit about which one we are using.
Depending on findings we may add the [external abdominal oblique](https://www.morningsideacupuncturenyc.com/external-abdominal-oblique-trigger-points) and [transverse abdominis](https://www.morningsideacupuncturenyc.com/transverse-abdominis-trigger-points), keep depth conservative over the peritoneum, and finish with a distal point such as ST36 so the treatment is not purely local.
ST23 Digestive and Stress Treatment at NYC's Highest-Rated Acupuncture Clinic
Morningside Acupuncture is the highest-rated acupuncture and dry needling clinic in New York City with over 500 five-star Google reviews, and our Upper West Side practice sees a steady stream of patients whose digestive symptoms and stress load travel together. We integrate classical point selection, including the supreme unity point, with trigger point dry needling of the abdominal wall when palpation calls for it. Every plan is built by a licensed acupuncturist and adjusted based on measurable change. Schedule your first session and see how your abdomen responds.
Schedule NowFrequently Asked Questions
What does ST23 feel like when needled?
Most people describe a dull, heavy, slightly spreading pressure under the needle rather than anything sharp. Because the abdomen is a sensitive area, the initial touch can feel more noticeable than on the arms or legs, and it is common to feel the belly soften or to hear gut sounds within a minute or two. Some patients notice a mild wave of warmth. Sharp, electric, or radiating sensations are not the goal and mean the needle should be repositioned, so tell your acupuncturist immediately if that happens.
Why needle the abdomen for digestive symptoms instead of only distal points on the arms and legs?
Because they do different things. Abdominal points like ST23 sit in the same spinal segment as the organs in question, so they can influence local muscle tone, abdominal wall tenderness, and segmental reflex circuits directly. Distal points such as ST36 tend to engage broader central and vagal pathways, and animal research suggests that stimulation at the abdomen and at the limbs can drive different autonomic responses (Uchida et al., 2017). Combining both is standard practice for that reason, and the classical texts arrived at the same pairing habit centuries earlier.
Can I press ST23 myself between sessions?
Yes, and it is one of the easier points to self-treat. Lie on your back with knees bent so the abdominal wall relaxes, find the spot two finger widths above the navel and about two finger widths out to the side, and press with the flat pads of two or three fingers rather than a fingertip. Use slow, moderate pressure that feels like firm reassurance rather than digging, hold for 30 to 60 seconds, then release, and repeat three to five times per side. Pairing each hold with a long exhale helps. Two or three short sessions a day is plenty. Skip it entirely if you have unexplained abdominal pain, fever, a hernia, recent abdominal surgery, or if you are pregnant, and check with your clinician first.
Is ST23 safe to needle?
In trained hands it is a routine point, but it is not a casual one. The main caution is depth: beneath the rectus abdominis lie the peritoneum, transverse colon, and small intestine, and classical texts specifically warn that deep needling in thin patients can enter the peritoneal cavity (Deadman et al., 2007). Practitioners scale depth to body size, avoid the area over hernias, surgical scars, or a distended or acutely painful abdomen, and use clean single-use needles. Pregnancy is a reason to avoid abdominal needling. Undiagnosed abdominal pain, weight loss, bleeding, or persistent vomiting should be evaluated medically before any acupuncture is considered.
Where exactly is ST23 located?
Stomach 23 is on the front of the abdomen, 2 cun above the umbilicus and 2 cun lateral to the anterior midline, level with CV10. To find it, measure roughly two thumb widths straight up from the top edge of the navel to reach the CV10 level, then move sideways along that line. The 2 cun line is easiest to locate by palpating the outer border of your rectus abdominis muscle, which becomes obvious when you lift your head slightly, and taking the midpoint between that border and the midline. ST23 is one in a vertical chain of Stomach channel points on the abdomen, sitting between ST22 above and ST24 below.
References
- Deadman, P., Al-Khafaji, M., & Baker, K. (2009). A manual of acupuncture. Journal of Chinese Medicine Publications.
- O'Connor, J., & Bensky, D. (Eds. & Trans.). (1981). Acupuncture: A comprehensive text. Shanghai College of Traditional Medicine. Eastland Press.
- Simons, D. G., Travell, J. G., & Simons, L. S. (1999). Travell & Simons' myofascial pain and dysfunction: The trigger point manual, Vol. 1: Upper half of body (2nd ed.). Williams & Wilkins.
- Uchida, S., Kagitani, F., & Sato-Suzuki, I. (2017). Somatoautonomic reflexes in acupuncture therapy: A review. Autonomic Neuroscience, 203, 1-8. https://doi.org/10.1016/j.autneu.2016.11.001
- Guo, Y., Wei, W., & Chen, J. D. Z. (2020). Effects and mechanisms of acupuncture and electroacupuncture for functional dyspepsia: A systematic review. World Journal of Gastroenterology, 26(19), 2440-2457. https://doi.org/10.3748/wjg.v26.i19.2440
- Pang, B., Jiang, T., Du, Y.-H., Li, J., Li, B., Hu, Y.-C., & Cai, Q.-H. (2016). Acupuncture for functional dyspepsia: What strength does it have? A systematic review and meta-analysis of randomized controlled trials. Evidence-Based Complementary and Alternative Medicine, 2016, 3862916. https://doi.org/10.1155/2016/3862916
- Manheimer, E., Cheng, K., Wieland, L. S., Min, L. S., Shen, X., Berman, B. M., & Lao, L. (2012). Acupuncture for treatment of irritable bowel syndrome. Cochrane Database of Systematic Reviews, 2012(5), CD005111. https://doi.org/10.1002/14651858.CD005111.pub3
- Xu, Z., Zhang, X., Shi, H., Liang, M., Ning, F., & Wang, Q. (2024). Efficacy of acupuncture for anxiety and depression in functional dyspepsia: A systematic review and meta-analysis. PLOS ONE, 19(3), e0298438. https://doi.org/10.1371/journal.pone.0298438
- Yang, X.-Y., Yang, N.-B., Huang, F.-F., Ren, S., & Li, Z.-J. (2021). Effectiveness of acupuncture on anxiety disorder: A systematic review and meta-analysis of randomised controlled trials. Annals of General Psychiatry, 20(1), 9. https://doi.org/10.1186/s12991-021-00327-5
- Zhao, Z. Q. (2008). Neural mechanism underlying acupuncture analgesia. Progress in Neurobiology, 85(4), 355-375. https://doi.org/10.1016/j.pneurobio.2008.05.004
- Vickers, A. J., Vertosick, E. A., Lewith, G., MacPherson, H., Foster, N. E., Sherman, K. J., Irnich, D., Witt, C. M., & Linde, K. (2018). Acupuncture for chronic pain: Update of an individual patient data meta-analysis. Journal of Pain, 19(5), 455-474. https://doi.org/10.1016/j.jpain.2017.11.005
Disclaimer: This web site is intended for educational and informational purposes only. Reading this website does not constitute providing medical advice or any professional services. This information should not be used for diagnosing or treating any health issue or disease. Those seeking medical advice should consult with a licensed physician. Seek the advice of a medical doctor or other qualified health professional for any medical condition. If you think you have a medical emergency, call 911 or go to the emergency room. No acupuncturist-patient relationship is created by reading this website or using the information. Morningside Acupuncture PLLC and its employees and contributors do not make any express or implied representations with respect to the information on this site or its use. For any legal interpretation of scope of practice in your state, consult a licensed attorney or regulatory authority.
Read more from our blog



