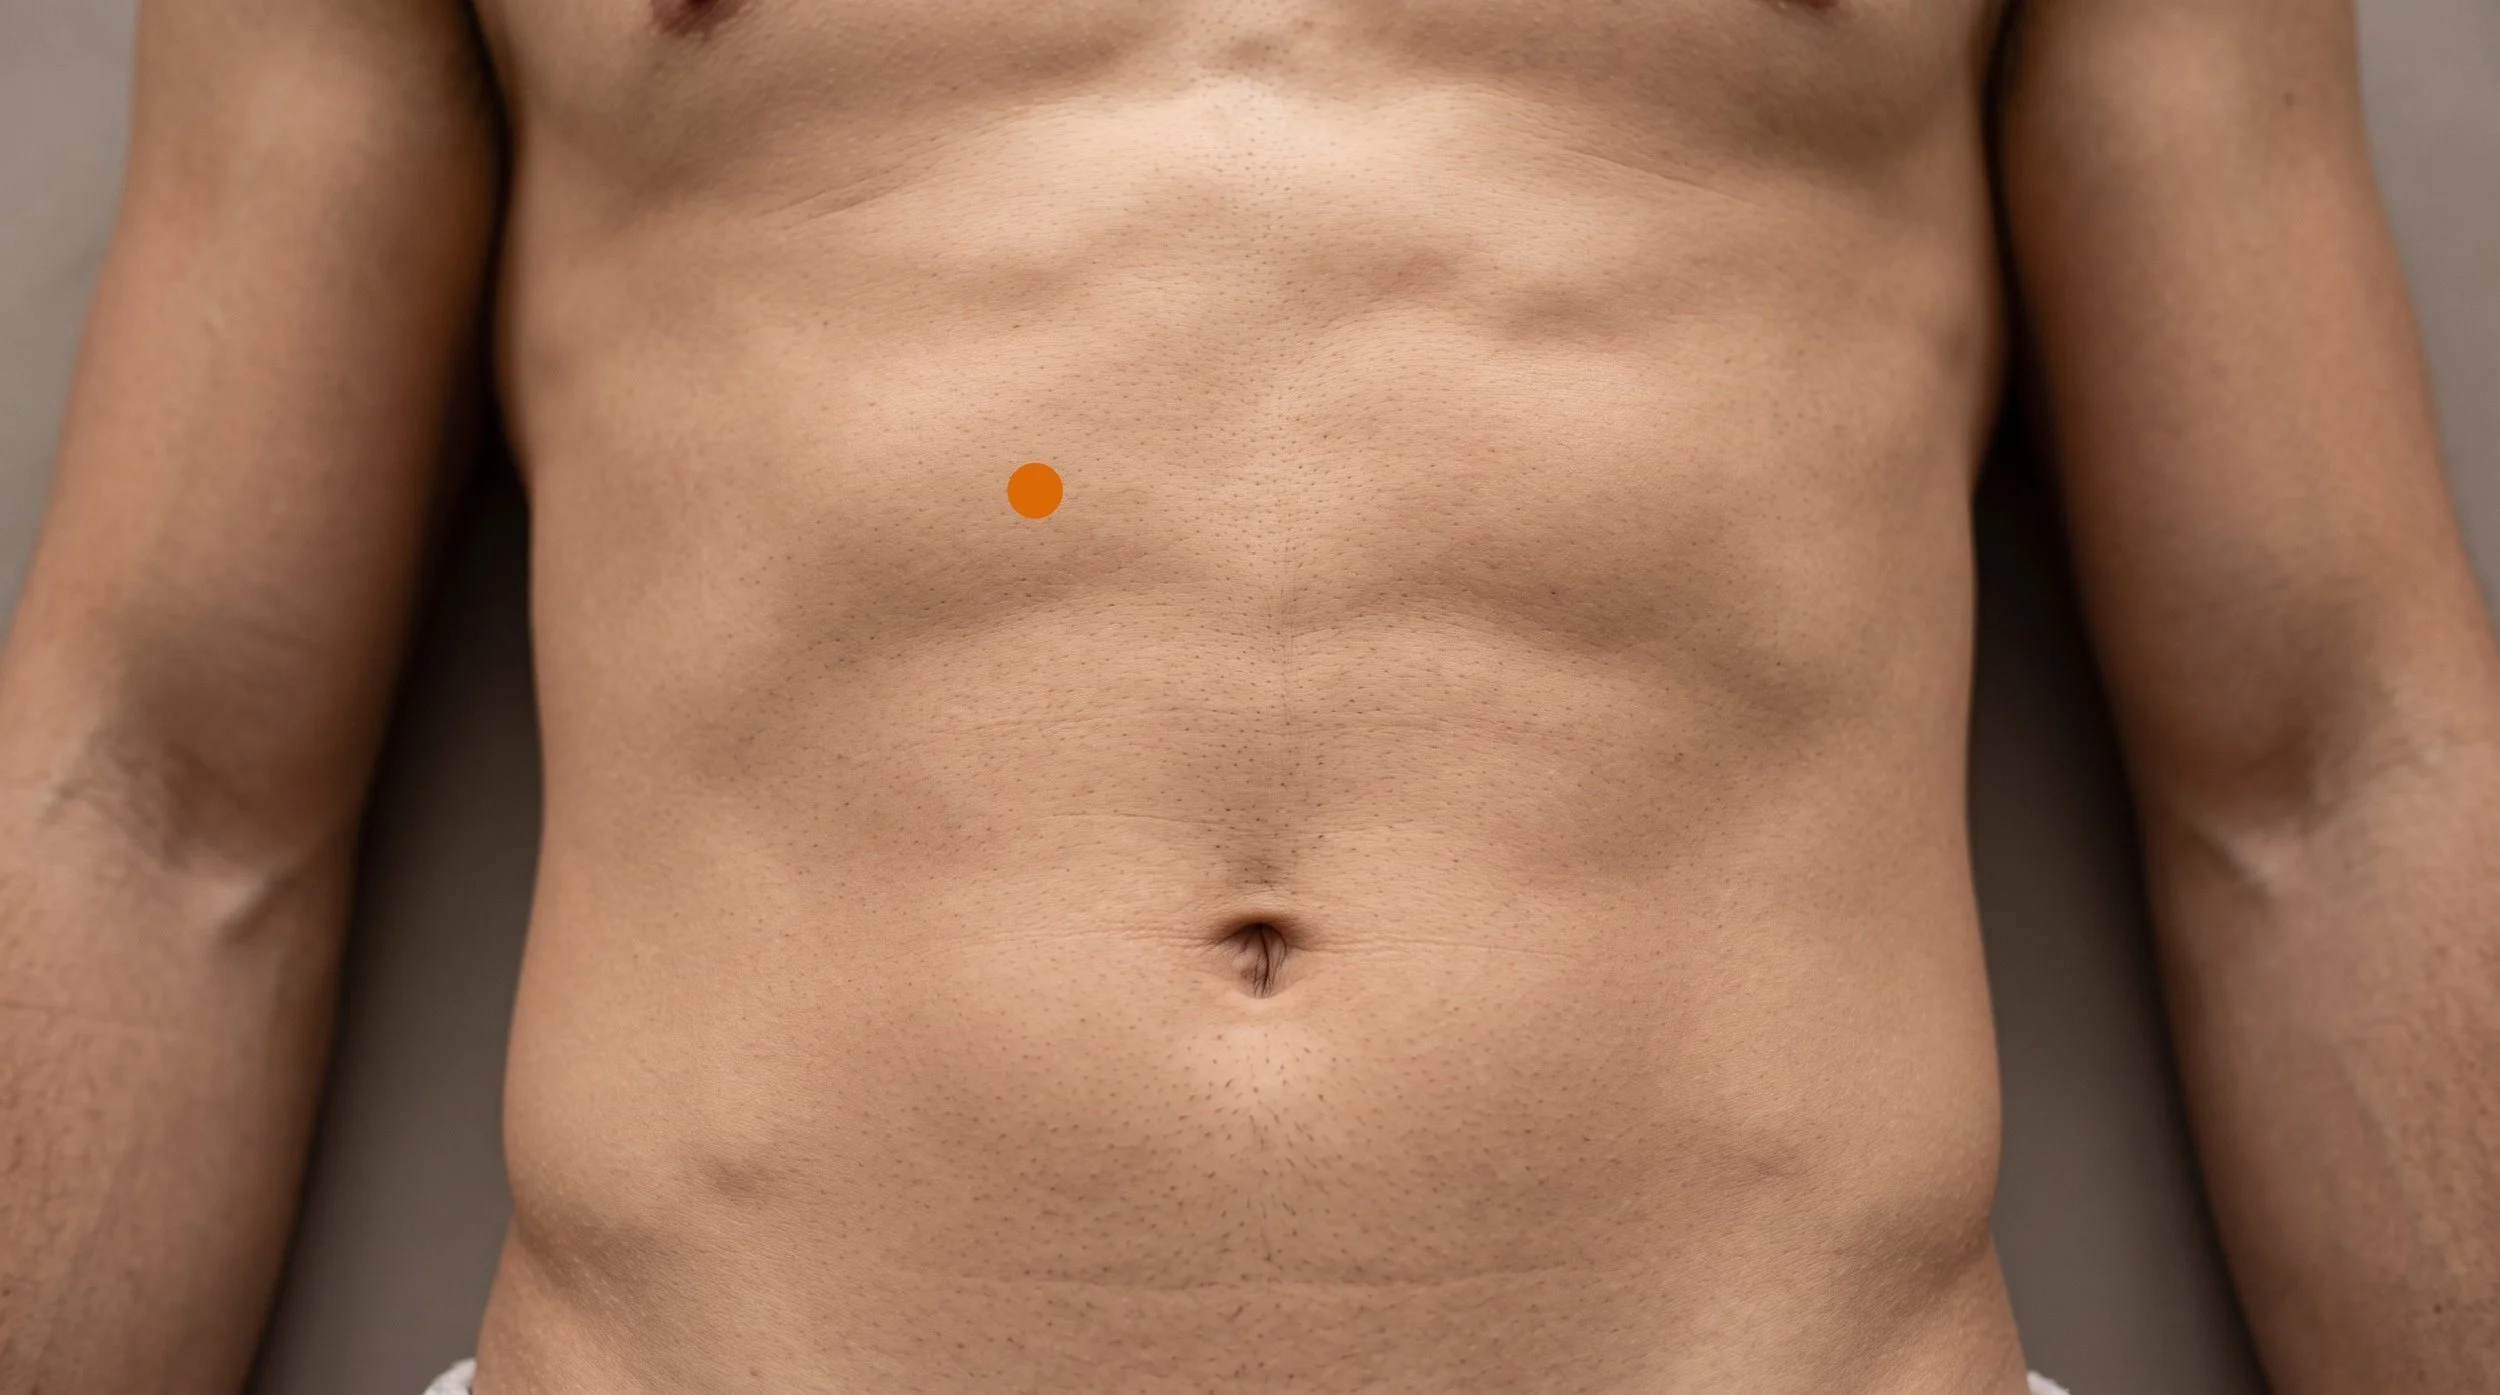
ST21 Acupuncture Point (Liangmen)
The Beam Gate Beside the Stomach's Mu Point: Anatomy, Segmental Mechanism, and Why ST21 Anchors Upper Abdominal Treatment
ST21 (Liangmen, often translated as Beam Gate or Beam Door) sits on the upper abdomen, 4 cun above the navel and 2 cun out from the midline, directly level with CV12. In plain terms, it is the point roughly halfway between your belly button and the bottom of the breastbone, then about two finger widths to the side, resting in the belly of the rectus abdominis over the stomach.
That geography is the whole story: the st21 acupuncture point is the lateral partner of CV12, the point clinicians reach for when epigastric pain is not neatly central but spreads sideways toward the rib edge, and when that pain comes bundled with fullness, bloating, and appetite changes. Stomach 21 is a workhorse rather than a famous point, and it earns its place through location, segmental innervation, and its long classical association with accumulation and distention below the ribs.
- Location and layers: ST21 lies 4 cun above the umbilicus and 2 cun lateral to the midline, level with CV12, on the line halfway between the midline and the palpable outer edge of the rectus abdominis (Deadman et al., 2007; Kim, 2010). The needle passes skin, subcutaneous fat, the anterior rectus sheath, and rectus abdominis fibers.
- Traditional attributions translated: classical sources describe ST21 as regulating qi and relieving pain, harmonizing the middle burner, transforming food accumulation, and lifting sunken qi in chronic diarrhea (Deadman et al., 2007). Read neurophysiologically, that cluster maps onto segmental modulation of upper gut sensation and autonomic tone rather than any literal flow of energy.
- Nerve story: the abdominal wall here is supplied by the anterior cutaneous and muscular branches of the lower intercostal nerves in roughly T8 territory, and stomach afferents reach the same thoracic spinal segments through the greater splanchnic pathway, which is the convergence that makes upper abdominal points viscerally relevant (Li et al., 2007; Yin & Chen, 2010).
- Point-specific physiology: in anesthetized animal work that directly compared body regions, ST21 was one of the abdominal points studied, and abdominal stimulation tended to reduce gastric motility through sympathetic spinal reflexes while limb points such as ST36 raised motility through vagal circuits, with effects appearing only when stimulation reached A-delta and C fiber thresholds (Li et al., 2006; Li et al., 2007).
- Research picture: trials of acupuncture for functional dyspepsia use multi-point protocols that commonly include upper abdominal points alongside CV12 and ST36, and results range from a cautious Cochrane conclusion limited by study quality to a large sham-controlled trial reporting better response rates in postprandial distress syndrome (Lan et al., 2014; Yang et al., 2020; Li et al., 2026).
- Clinical framing and de qi: ST21 is usually needled perpendicular 1 to 1.5 cun, shallower in thin patients, and depth stays conservative because deep insertion can reach the peritoneal cavity and, on the right, an enlarged liver (Deadman et al., 2007). De qi here is typically a dull, spreading fullness or heaviness under the needle rather than the sharp electric quality patients report at limb points.
Dealing With Epigastric Pain, Bloating, or Post-Meal Fullness?
Upper abdominal discomfort often has more than one driver: gut sensitivity, guarded abdominal wall muscles, and a nervous system stuck in a protective pattern. At Morningside Acupuncture we use ST21 with CV12 and ST36 as part of a plan that also assesses the rectus abdominis and obliques for tender bands that can mimic stomach symptoms. Every plan starts with a full intake, and we always coordinate with your gastroenterologist when a workup is underway. Schedule a visit and we will map out what is actually driving your symptoms.
Schedule NowAnatomy of ST21: Why the Rectus Abdominis Over the Stomach Is Such an Important Location
From the surface inward, a needle at ST21 passes through skin, a variable layer of subcutaneous fat, the anterior rectus sheath, and then the fibers of the rectus abdominis, frequently near one of its tendinous intersections. Deeper still lie the posterior sheath, transversalis fascia, and the peritoneum, with the stomach and, on the right side, the lower edge of the liver sitting beneath.
The rectus at this level is loaded by everything that asks the trunk to brace: coughing, lifting, sit-ups and planks, prolonged seated flexion at a desk, and the low-grade guarding that follows abdominal surgery or a long stretch of gut discomfort. That guarding matters clinically, because a chronically shortened, tender upper rectus can generate a deep ache patients describe in stomach terms.
The nerve geography explains why a point on the belly wall can influence how the stomach feels. The abdominal wall here is innervated by branches of the lower intercostal nerves in roughly T8 territory, while sensory traffic from the stomach travels with sympathetic splanchnic fibers into the mid-thoracic dorsal horn. Somatic and visceral afferents converge on shared spinal neurons, which is the mechanism behind referred epigastric tenderness and also the reason segmental needling can change how that region is processed centrally (Li et al., 2007; Yin & Chen, 2010).
Needle stimulation additionally recruits descending inhibitory pathways from the brainstem, one of the better-characterized mechanisms of acupuncture analgesia (Zhao, 2008), and manual acupuncture at abdominal points has been shown in animal models to shift gastric motor activity through segmental sympathetic reflexes when stimulation is strong enough to engage small-diameter afferents (Li et al., 2006).
The safety-relevant structures are the superior epigastric vessels running within the rectus sheath, the peritoneal cavity below the muscle, and the liver on the right in patients with hepatomegaly. Classical texts therefore set perpendicular insertion at 1 to 1.5 cun and flag two cautions: deep needling can penetrate the peritoneal cavity in thin patients, and deep needling at the right ST21 can reach an enlarged liver (Deadman et al., 2007). Other references keep the depth closer to 0.8 to 1.0 cun and note that moxibustion can be applied (Kim, 2010).
In practice, depth is chosen from body composition rather than a fixed number, the abdomen is needled with the patient relaxed and breathing quietly, and in patients with a narrow subcostal angle where the point falls on the rib margin, the options are to shift slightly medially, angle transversely along the costal edge, or use a different point (Deadman et al., 2007).
Related Rectus Abdominis Trigger Points Related Stomach ChannelST21 at a Glance: Classification, Location, and Clinical Use
| Category | Detail |
|---|---|
| Traditional Name | Liangmen (Beam Gate, also translated Beam Door or Door of the Beam) |
| Channel Classification | Twenty-first point of the Stomach channel of Foot Yangming, on the upper abdomen |
| Point Categories | No five-shu, mu, luo, xi-cleft, hui-meeting, or extraordinary vessel crossing designation is recorded for this point in the reference literature. It is classified simply as a Stomach channel point of the upper abdomen, positioned level with CV12, the Stomach's front-mu point, which is why the two are so often used together. |
| Precise Location | On the upper abdomen, 4 cun superior to the umbilicus and 2 cun lateral to the anterior midline, level with CV12. The 2 cun line sits halfway between the midline and the palpable lateral border of the rectus abdominis. A practical check: the umbilicus to the sternocostal angle spans 8 cun, so halving that distance gives the level of ST21, and halving the midline-to-nipple-line distance gives the 2 cun lateral measurement (Deadman et al., 2007; Kim, 2010). |
| Tissue Stimulated | Skin and subcutaneous tissue, anterior rectus sheath, and the belly of the rectus abdominis, with the abdominal obliques and transverse abdominis lateral and deep to it. Innervation is from lower intercostal nerve branches in approximately T8 territory. |
| Needle Depth / Direction | Perpendicular insertion 1 to 1.5 cun, with shallower depths (roughly 0.8 to 1.0 cun) used in thin patients and in most routine treatment. Transverse or oblique angling along the costal margin is an option when a narrow subcostal angle pushes the point onto the ribs. Moxibustion is traditionally permitted. |
| De Qi Sensation | A dull, spreading fullness, heaviness, or mild ache in the epigastrium, sometimes traveling toward the rib edge or across toward the midline. Abdominal de qi is usually softer and slower to build than at limb points, and the needle moves gently with the breath. |
| Primary Clinical Uses | Epigastric pain, especially when it spreads laterally under the ribs; upper abdominal distention and post-meal fullness; nausea and poor appetite; traditionally, borborygmus and chronic loose stools with undigested food; and stomach-region discomfort treated alongside CV12 in modern protocols. |
| Common Point Combinations |
|
In A Manual of Acupuncture, Deadman and colleagues present ST21 as a point traditionally credited with regulating qi and easing pain, harmonizing the middle burner, transforming stagnant accumulation, and raising sunken qi to check diarrhea. Its classical indication list clusters into three groups: pain and fullness in the epigastrium and along the lateral costal region, digestive complaints such as vomiting, poor appetite and rumbling in the belly, and chronic loose stools containing undigested food.
The commentary is explicit that Liangmen was favored over, or added to, CV12 when abdominal pain was severe and skewed toward the sides rather than the center. The name itself is the striking part: liang refers to one of the five accumulations described in the Classic of Difficulties, a form said to involve a palpable mass in the region below the heart, meaning the epigastrium.
These are traditional attributions rather than physiological descriptions, but the pattern they encode, sideways-spreading upper abdominal pain with a sense of blockage and a firm, guarded belly wall, is a presentation any modern clinician still recognizes at the treatment table.
Why ST21 Is Used for Post-Meal Bloating and Rib-Edge Tightness, Not Just Stomach Pain
The most useful way to understand ST21 is segmentally. The abdominal wall at this level and the stomach itself send sensory information into overlapping mid-thoracic spinal segments, the stomach by way of splanchnic sympathetic afferents and the wall by way of the lower intercostal nerves.
When two inputs converge on the same spinal neurons, irritation in one can be felt as tenderness in the other, which is why upper abdominal complaints so often come with a taut, sore band of rectus abdominis, and why pressing that band can reproduce a symptom patients had assumed was purely digestive (Li et al., 2007; Yin & Chen, 2010). Needling into that shared segment gives the nervous system a competing, well-localized input in exactly the territory where the confusion is happening.
There is also a measurable autonomic side. In carefully controlled animal experiments comparing stimulation at different body regions, abdominal points including ST21 tended to reduce gastric motor activity through sympathetic spinal reflexes, while limb points such as ST36 tended to increase it through vagal circuits routed through the brainstem, and neither effect appeared unless stimulation was strong enough to recruit A-delta and C fibers (Li et al., 2006; Li et al., 2007).
That is a tidy neurophysiological account of why classical practice pairs abdominal points with leg points: the two act on different arms of the autonomic nervous system, and combining them may allow a more balanced response than either alone. Broader reviews of acupuncture in gastrointestinal motility disorders reach a similar conclusion, that point location and stimulation parameters, not the needle alone, determine the direction of the effect (Guo et al., 2020).
Layered on top of the segmental effects is the general analgesic machinery of needling: activation of descending inhibitory pathways from the periaqueductal gray and rostral ventromedial medulla, with endogenous opioid and monoamine involvement (Zhao, 2008). This is the same system implicated in the modest but persistent benefits seen across chronic pain conditions in individual patient data meta-analysis (Vickers et al., 2018).
For a patient, the practical translation is that ST21 may reduce how loudly the upper abdomen registers discomfort while also softening the muscular guarding that keeps the region tense after meals.
What the Research Shows for ST21
A fair reading of the literature starts with a caveat: no trial has isolated ST21. Studies of acupuncture for functional dyspepsia and related upper gut complaints test whole protocols, typically CV12 with abdominal and leg points, so ST21's contribution is inferred from the prescriptions used and from mechanism work that stimulated the point directly in animal models. Within those limits, the clinical evidence is mixed but improving, with older reviews constrained by poor methodology and newer sham-controlled work reporting more convincing symptom differences. The findings below are best read as support for the overall approach rather than proof of any single point's effect.
| Study | Type | Focus | Key Finding |
|---|---|---|---|
| Lan et al., 2014 | Cochrane systematic review | Manual acupuncture and electroacupuncture for functional dyspepsia (7 trials, 542 participants) | Acupuncture performed similarly to prokinetic medications and better than sham in some comparisons, but the authors judged the evidence too low in quality to draw a firm conclusion about efficacy or safety. |
| Yang et al., 2020 | Multicenter randomized sham-controlled trial | Postprandial distress syndrome, 12 sessions over 4 weeks | Acupuncture produced higher response rates and higher elimination rates of all three cardinal symptoms than sham, with benefit maintained across 12 weeks of follow-up. |
| Li et al., 2026 | Updated systematic review and meta-analysis (23 RCTs, 2,454 participants) | Acupuncture for functional dyspepsia symptoms and quality of life | Moderate to high certainty evidence suggested acupuncture probably improves dyspepsia symptom scores and quality of life compared with sham, without an increase in adverse events. |
| Li et al., 2007 | Controlled animal neurophysiology study | Gastric motility responses to stimulation at abdominal points including ST21 versus limb points | Segmental abdominal stimulation inhibited gastric motility through sympathetic pathways while limb stimulation facilitated it through vagal pathways, and only stimulation above A-delta and C fiber thresholds produced clear effects. |
| Li et al., 2006 | Experimental study of acupoint-specific responses | Patterns of gastric motility change across different stimulation sites and intensities | The direction of the motility response varied systematically with body region and stimulus strength, supporting an autonomic reflex model rather than a uniform effect of needling. |
| Guo et al., 2020 | Systematic review of effects and mechanisms | Acupuncture and electroacupuncture for functional dyspepsia | Symptom improvements were reported alongside changes in gastric accommodation, motility, and autonomic measures, though protocols and outcome measures varied widely between studies. |
| Vickers et al., 2018 | Individual patient data meta-analysis | Acupuncture for chronic pain conditions (not gastrointestinal specific) | Acupuncture was associated with modest benefits over both sham and no-acupuncture controls, with effects that persisted over time. |
Want Digestive Care That Respects the Evidence?
We are direct about what the research supports and what it does not: reviews of acupuncture for functional dyspepsia show promise but also real limitations in study quality. Our approach uses ST21 within tested multi-point protocols, tracks your symptoms week to week, and adjusts rather than repeating the same prescription indefinitely. If four to six sessions are not moving the needle, we say so and change course. Book an appointment to get a clear, measurable plan.
Schedule NowST21 in the Context of Trigger Point Work
ST21 sits directly in the upper rectus abdominis, which makes it one of the clearest examples of a classical point and a myofascial target occupying the same real estate. Travell and Simons documented that trigger points in the abdominal wall can produce pain that patients and clinicians alike interpret as visceral, including upper abdominal aching, a sense of fullness, nausea, and heartburn-like discomfort, and that abdominal wall and viscera can drive each other in both directions (Simons et al., 1999).
At Morningside we palpate the rectus above and below the level of ST21, along with the [external oblique](https://www.morningsideacupuncturenyc.com/external-abdominal-oblique-trigger-points) at the rib edge, before deciding whether a given session should emphasize channel points, muscular targets, or both.
In practice the two approaches use the same needle and often the same site. If pressing at the st 21 abdomen location reproduces the patient's familiar symptom and a taut band is palpable, we treat it as a myofascial target with careful, shallow needling and appropriate depth control, then add CV12, [ST36](https://www.morningsideacupuncturenyc.com/blog/st36-acupuncture-point), and [PC6](https://www.morningsideacupuncturenyc.com/blog/pc6-acupuncture-point) to address the visceral and autonomic side.
If the abdominal wall is quiet on palpation and symptoms are clearly digestive, ST21 is used as a segmental point in a broader protocol. Either way, abdominal needling is done with conservative depth, a relaxed patient, and clear communication, and we refer out promptly when the presentation suggests anything requiring medical workup.
ST21 Digestive and Abdominal Pain Treatment at NYC's Highest-Rated Acupuncture Clinic
Morningside Acupuncture is the highest-rated acupuncture and dry needling clinic in New York City with over 500 five-star Google reviews. Our licensed acupuncturists combine classical point selection such as Liangmen with CV12 alongside modern trigger point needling of the abdominal wall for patients whose epigastric pain has both a visceral and a muscular component. Sessions are unhurried, safety-first, and explained in plain language. Schedule your visit and see why so many New Yorkers make this their home clinic.
Schedule NowFrequently Asked Questions
What does ST21 feel like when needled?
Most people describe a dull, spreading fullness or a heavy pressure under the needle rather than a sharp sensation. It may travel a short distance toward the midline or out toward the rib edge, and it often builds slowly over the first minute. Because the abdomen moves with breathing, you may notice the needle shifting slightly as you inhale, which is normal. Sharp, burning, or radiating pain is not the goal, and it should be reported right away so the needle can be adjusted or withdrawn.
Why needle the abdomen for stomach symptoms instead of only using points on the arms and legs?
Because they do different things. Abdominal points such as ST21 sit in the same spinal segments as the stomach itself, so they act on the local convergence of visceral and somatic input and on segmental sympathetic reflexes, while limb points such as ST36 and PC6 tend to work through vagal circuits routed through the brainstem (Li et al., 2007). Classical practice arrived at the same conclusion empirically, pairing epigastric points with distal points in almost every stomach protocol. Using both gives a broader handle on the problem than either alone.
Can I press ST21 myself between sessions?
Yes, acupressure at this location is reasonable for most people. Find the midpoint between your navel and the bottom of your breastbone, then move about two finger widths to the side, and press with the pads of two fingers at a moderate, tolerable pressure while your abdomen is relaxed. Hold steady for 30 to 60 seconds, or make small circles for the same duration, then repeat on the other side, two or three rounds per session and once or twice a day. Do it seated or lying down with knees bent, breathe slowly rather than holding your breath, and stop if the pressure creates sharp pain, nausea that worsens, or any pulsing sensation. Avoid it right after a large meal, and skip abdominal pressure entirely if you are pregnant, have had recent abdominal surgery, or have an undiagnosed abdominal mass or new severe pain.
Is ST21 safe to needle?
In trained hands it is a routine and well-tolerated point, but it is one where depth discipline matters. Classical needling depth is perpendicular 1 to 1.5 cun, and the standard cautions are that deep insertion in thin patients can reach the peritoneal cavity and that deep insertion on the right side can reach an enlarged liver (Deadman et al., 2007). Practitioners therefore choose depth from body habitus rather than a fixed number, angle away from risk when needed, and avoid the point on the rib margin. Abdominal needling is generally avoided in pregnancy, over recent surgical sites, over hernias, and in anyone with undiagnosed acute abdominal pain, which always warrants medical evaluation first.
Where exactly is ST21 located?
Stomach 21 is on the upper abdomen, 4 cun above the center of the umbilicus and 2 cun lateral to the anterior midline, level with CV12. Two measuring tricks make it easy: the distance from the navel to the sternocostal angle is 8 cun, so half of that gives the correct level, and the distance from midline to the nipple line is 4 cun, so half of that gives the 2 cun lateral measurement (Kim, 2010). The 2 cun line falls roughly halfway between the midline and the outer edge of the rectus abdominis, which you can usually feel by having someone lift their head slightly against resistance. In patients with a narrow rib angle, this level can land on the costal margin, in which case the point is located slightly more medially or another point is chosen.
References
- Deadman, P., Al-Khafaji, M., & Baker, K. (2009). A manual of acupuncture. Journal of Chinese Medicine Publications.
- Kim, H. (2008). Handbook of Oriental medicine (3rd ed.). Harmony & Balance Press.
- Maciocia, G. (2005). The foundations of Chinese medicine: A comprehensive text for acupuncturists and herbalists (2nd ed.). Elsevier Churchill Livingstone.
- O'Connor, J., & Bensky, D. (Eds. & Trans.). (1981). Acupuncture: A comprehensive text. Shanghai College of Traditional Medicine. Eastland Press.
- Maciocia, G. (2006). The channels of acupuncture: Clinical use of the secondary channels and eight extraordinary vessels. Churchill Livingstone Elsevier.
- Simons, D. G., Travell, J. G., & Simons, L. S. (1999). Travell & Simons' myofascial pain and dysfunction: The trigger point manual, Vol. 1: Upper half of body (2nd ed.). Williams & Wilkins.
- Lan, L., Zeng, F., Liu, G. J., Ying, L., Wu, X., Liu, M., & Liang, F. R. (2014). Acupuncture for functional dyspepsia. Cochrane Database of Systematic Reviews, 2014(10), CD008487. https://doi.org/10.1002/14651858.CD008487.pub2
- Yang, J. W., Wang, L. Q., Zou, X., Yan, S. Y., Wang, Y., Zhao, J. J., Tu, J. F., Wang, J., Shi, G. X., Hu, H., Zhou, W., Du, Y., & Liu, C. Z. (2020). Effect of acupuncture for postprandial distress syndrome: A randomized clinical trial. Annals of Internal Medicine, 172(12), 777-785. https://doi.org/10.7326/M19-2880
- Li, X. X., Hu, Z. Y., Li, Z. C., Tang, J., Liu, Y. Y., Zeng, D. H., Zhou, Q. Q., Ma, W. B., Lan, L., & Wang, L. (2026). Efficacy and safety of acupuncture for functional dyspepsia: An updated meta-analysis of randomized controlled trials. Frontiers in Medicine, 1718632. https://doi.org/10.3389/fmed.2026.1718632
- Li, Y. Q., Zhu, B., Rong, P. J., Ben, H., & Li, Y. H. (2007). Neural mechanism of acupuncture-modulated gastric motility. World Journal of Gastroenterology, 13(5), 709-716. https://doi.org/10.3748/wjg.v13.i5.709
- Li, Y. Q., Zhu, B., Rong, P. J., Ben, H., & Li, Y. H. (2006). Effective regularity in modulation on gastric motility induced by different acupoint stimulation. World Journal of Gastroenterology, 12(47), 7642-7648. https://doi.org/10.3748/wjg.v12.i47.7642
- Guo, Y., Wei, W., & Chen, J. D. Z. (2020). Effects and mechanisms of acupuncture and electroacupuncture for functional dyspepsia: A systematic review. World Journal of Gastroenterology, 26(19), 2440-2457. https://doi.org/10.3748/wjg.v26.i19.2440
- Yin, J., & Chen, J. D. Z. (2010). Gastrointestinal motility disorders and acupuncture. Autonomic Neuroscience, 157(1-2), 31-37. https://doi.org/10.1016/j.autneu.2010.03.007
- Zhao, Z. Q. (2008). Neural mechanism underlying acupuncture analgesia. Progress in Neurobiology, 85(4), 355-375. https://doi.org/10.1016/j.pneurobio.2008.05.004
- Vickers, A. J., Vertosick, E. A., Lewith, G., MacPherson, H., Foster, N. E., Sherman, K. J., Irnich, D., Witt, C. M., & Linde, K. (2018). Acupuncture for chronic pain: Update of an individual patient data meta-analysis. Journal of Pain, 19(5), 455-474. https://doi.org/10.1016/j.jpain.2017.11.005
Disclaimer: This web site is intended for educational and informational purposes only. Reading this website does not constitute providing medical advice or any professional services. This information should not be used for diagnosing or treating any health issue or disease. Those seeking medical advice should consult with a licensed physician. Seek the advice of a medical doctor or other qualified health professional for any medical condition. If you think you have a medical emergency, call 911 or go to the emergency room. No acupuncturist-patient relationship is created by reading this website or using the information. Morningside Acupuncture PLLC and its employees and contributors do not make any express or implied representations with respect to the information on this site or its use. For any legal interpretation of scope of practice in your state, consult a licensed attorney or regulatory authority.
Read more from our blog



