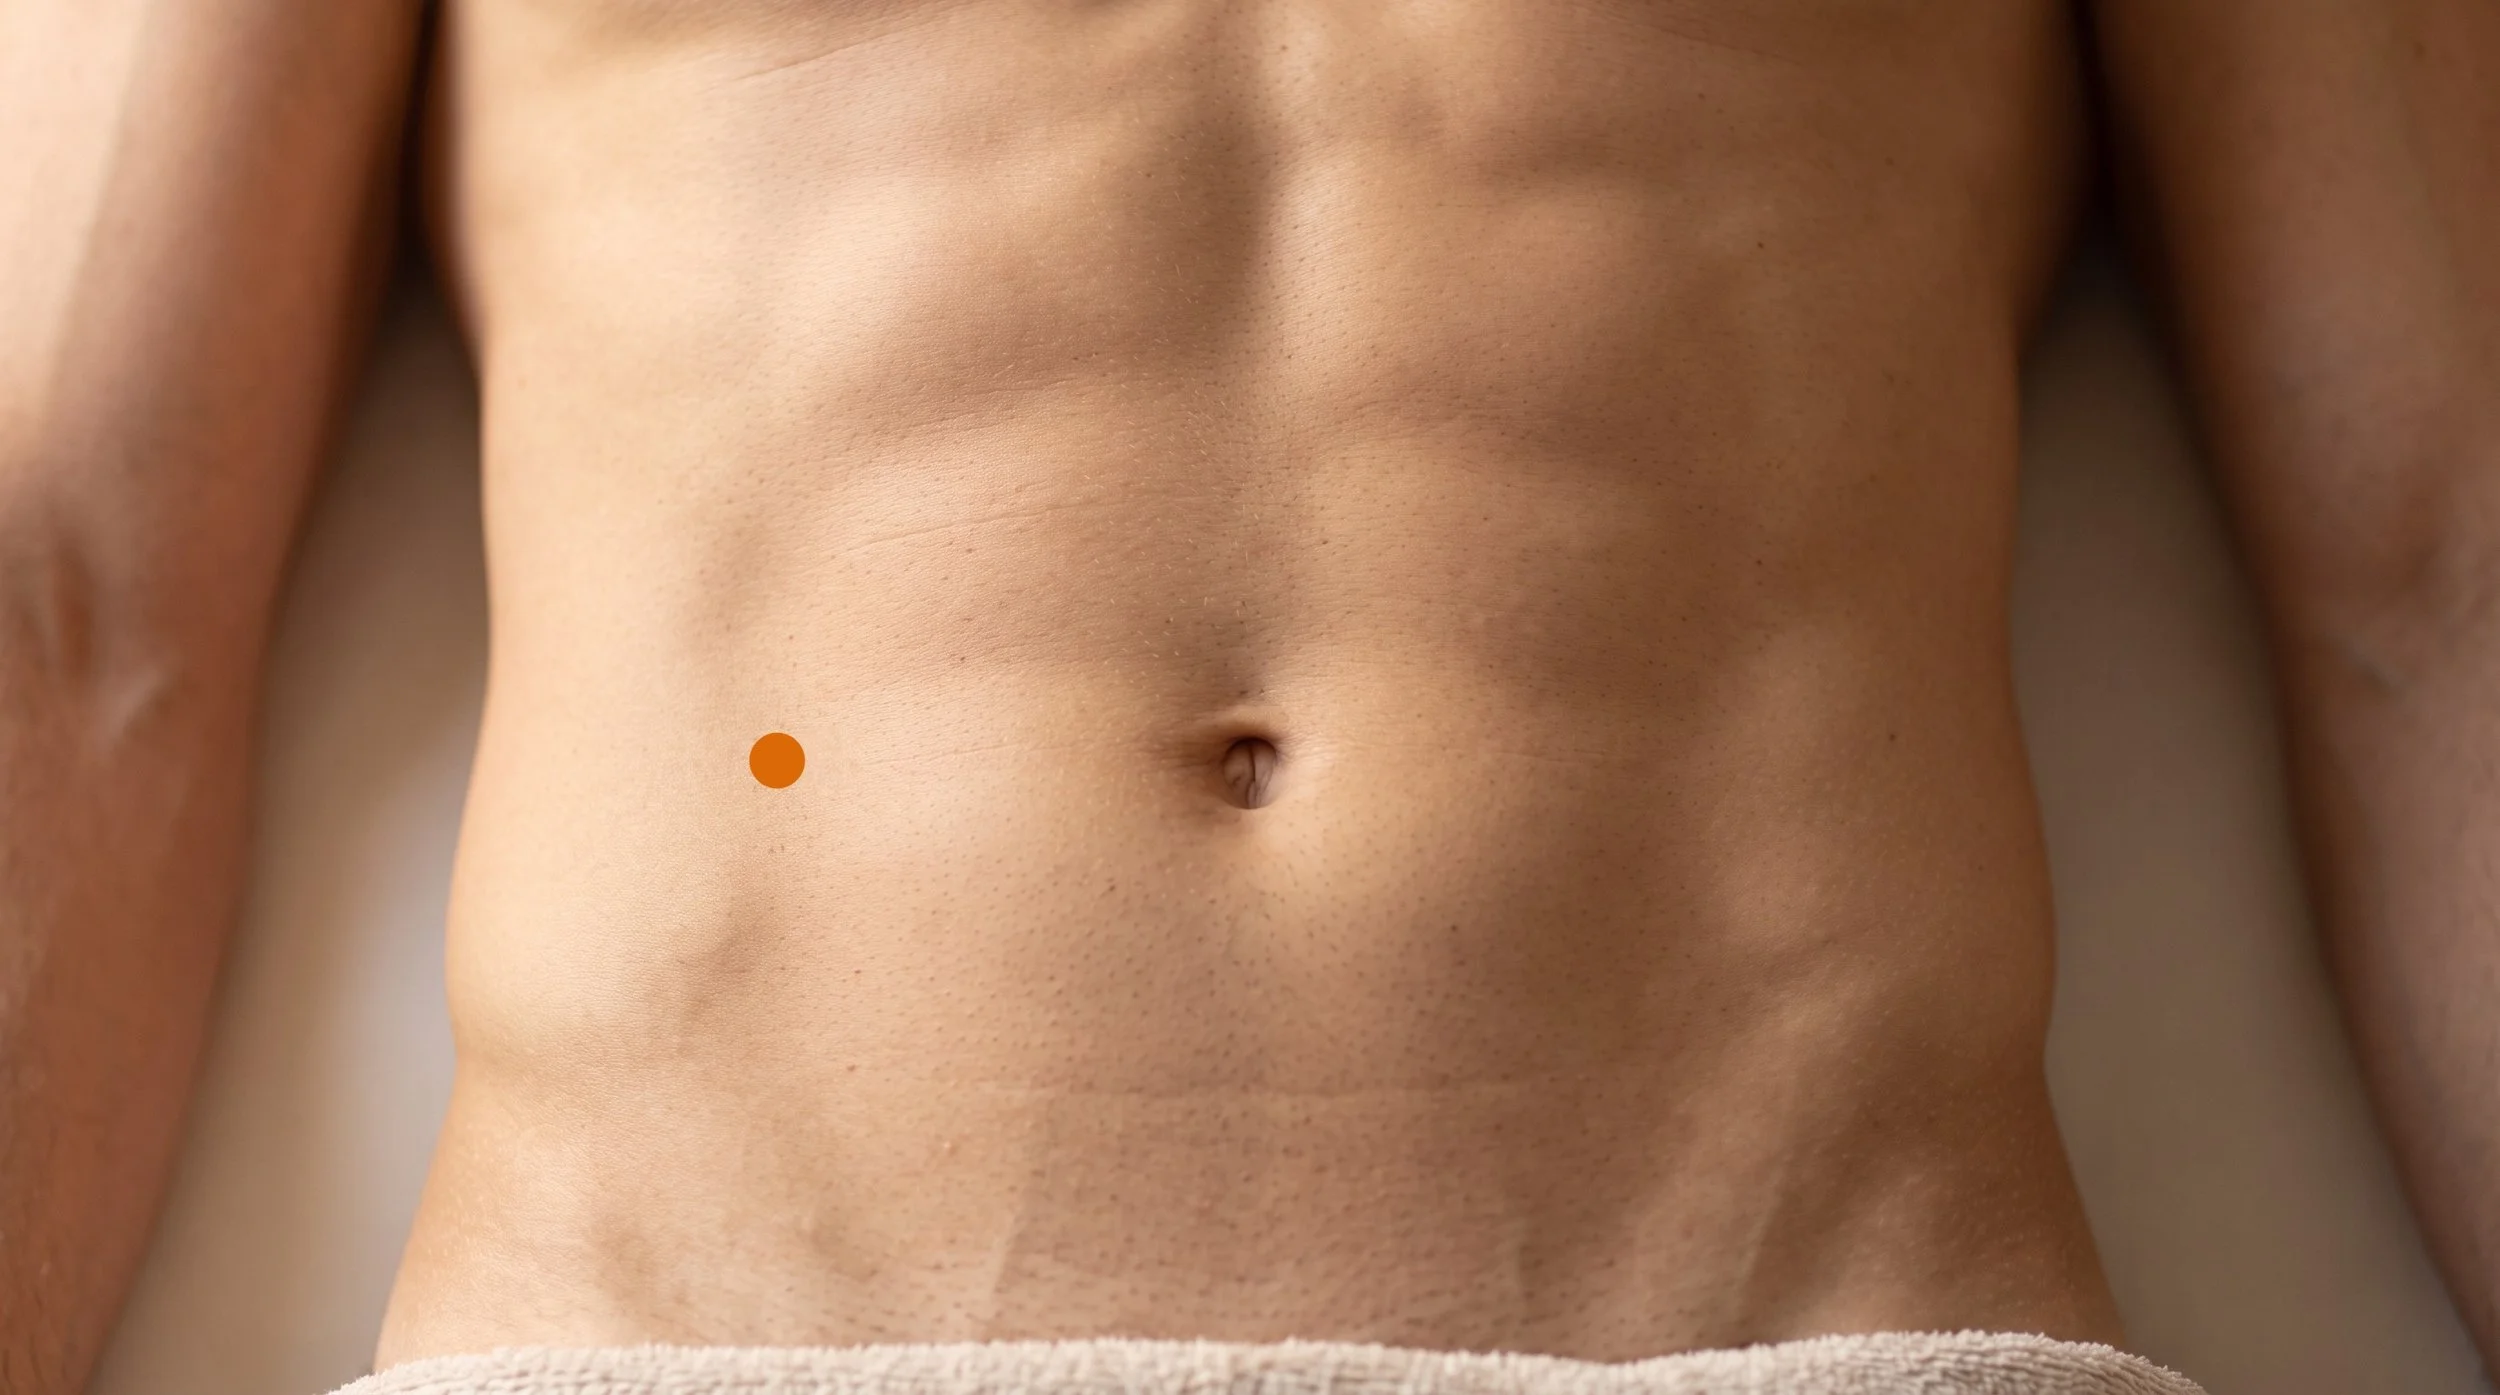
SP15 Acupuncture Point (Daheng)
The Great Horizontal Point Beside the Navel: Anatomy, Segmental Gut Reflexes, and Why SP15 Anchors Acupuncture for Constipation and Sluggish Digestion
SP15 (Daheng, often translated as Great Horizontal) sits on the abdomen at the same height as the navel, tucked into the soft groove at the outer edge of the rectus abdominis muscle, roughly 4 cun lateral to the midline on each side. It belongs to the Spleen channel and is classified in the classical literature as a meeting point of that channel with the Yin Linking vessel, which is one reason it turns up in formulas that reach well beyond the belly.
Clinically, the sp15 acupuncture point is best known as a bowel point: practitioners reach for spleen 15 when digestion is slow, gassy and hard to move, and it is the navel-level point traditionally favored for constipation, while its neighbor ST25 carries more of the diarrhea reputation. Because it lies directly over colon in a T10 to T11 segmental field, sp 15 abdomen needling is a good example of how a surface point and a visceral target can share the same spinal address.
- Location and layers: SP15 is level with the center of the umbilicus at the lateral border of the rectus abdominis, normally 4 cun lateral to the midline, which means the needle passes through skin, subcutaneous fat and the aponeurotic junction of the abdominal wall muscles rather than through a thick muscle belly.
- Traditional attribution: classical sources list Daheng as a crossing point of the Spleen channel with the Yin Linking vessel and describe actions such as moving qi in the intestines, resolving damp and relieving abdominal pain. Read in modern terms, those descriptions map onto a point used to modulate bowel motility and abdominal wall discomfort.
- Mechanism: strong needling of the abdominal wall drives segmental spinal reflexes that reach the gut through sympathetic pathways, while limb stimulation tends to recruit vagal pathways, a pattern demonstrated repeatedly in animal recordings (Noguchi, 2008; Ma, 2020). This is the clearest physiological reason abdominal and leg points are usually combined.
- Research: the largest sham-controlled acupuncture trial in this area found that eight weeks of electroacupuncture at abdominal and leg points increased complete spontaneous bowel movements in chronic severe functional constipation, with benefit persisting for weeks after treatment ended (Liu et al., 2016), while earlier reviews were positive but methodologically weak (Zhang et al., 2013).
- Clinical framing: SP15 is rarely used alone. It is typically one element of a bowel-regulating group with ST25, ST36 and back points, and results tend to build over a course of sessions rather than after a single treatment.
- De qi: patients usually describe a dull, spreading fullness or a mild heaviness under the needle rather than sharpness, and audible gurgling of the intestines during the session is common and harmless.
Struggling With Constipation, Bloating or a Sluggish Gut?
At Morningside Acupuncture we treat slow, uncomfortable digestion with a plan rather than a single point, and SP15 is often part of the abdominal group we use alongside leg and back points. We take a careful history first, because bowel symptoms deserve a proper workup before anyone reaches for a needle. Treatment is gentle, the depth over the abdomen stays conservative, and we track changes week to week. Schedule a visit to see whether this approach fits your situation.
Schedule NowAnatomy of SP15: Why the Lateral Border of the Rectus Abdominis at the Navel Is Such an Important Location
Find the center of the navel, then travel straight out to the side until your fingertip drops into the soft channel just past the firm edge of the rectus abdominis. That groove is SP15. Under the fingertip there is skin and a variable layer of subcutaneous fat, then the fascial junction where the aponeuroses of the external oblique, internal oblique and transversus abdominis meet and wrap the rectus sheath. The muscle fibers themselves lie medial to the point, and the flat aponeurotic sheet lies directly beneath it.
This region takes load every time you sit up, twist, brace, cough or hold your breath under exertion, and it is frequently altered by abdominal surgery, hernia repair, pregnancy and long hours of seated flexion, all of which can leave the tissue at the rectus border tender and guarded.
The segmental story is what makes this location interesting. The skin and muscle at umbilical level are supplied by the thoracoabdominal nerves around T10 and T11, and the same spinal segments receive visceral afferent traffic from the colon that runs beneath the point (ascending colon on the right, descending colon on the left). That shared spinal address is the basis of viscerosomatic convergence: input from the belly wall and input from the bowel arrive at overlapping dorsal horn neurons, so stimulating one can change how the system processes the other.
Needling recruits small-diameter group III and IV afferents, which trigger segmental reflexes that reach the gut through sympathetic outflow, while stimulation at the limbs tends to engage vagal pathways instead (Noguchi, 2008; Ma, 2020).
Beyond the local reflex, needling also activates descending inhibitory systems in the brainstem and spinal cord that use opioid, serotonergic and noradrenergic transmitters to damp nociceptive signaling (Zhao, 2008).
Depth discipline matters here more than at most points. Beneath the aponeurosis lie the transversalis fascia, preperitoneal fat, peritoneum and bowel, so classical texts set perpendicular insertion at roughly 0.5 to 1 cun and warn that in thin patients deep needling can enter the peritoneal cavity, and that a substantially enlarged spleen or liver changes what sits under the needle (Deadman and colleagues' A Manual of Acupuncture). Other clinical manuals cite a similar working range of about 0.7 to 1.2 cun.
Practically, we palpate the abdominal wall first, choose depth based on body habitus rather than a fixed number, keep the angle perpendicular or slightly oblique, and avoid the point entirely over surgical mesh, unexplained masses, acute abdominal pain or in pregnancy.
Related Rectus Abdominis Trigger Points Related Spleen ChannelSP15 at a Glance: Classification, Location, and Clinical Use
| Category | Detail |
|---|---|
| Traditional Name | Daheng (Great Horizontal, also rendered as Big Horizontal Stroke) |
| Channel Classification | Spleen channel of the foot Taiyin, abdominal segment, the fifteenth point of the channel |
| Point Categories | Meeting (crossing) point of the Spleen channel with the Yin Linking vessel (Yin Wei Mai), listed alongside SP13, SP16, KI9, LR14, CV22 and CV23 as an intersection of that vessel. It is not a five-shu, yuan-source or hui-meeting point. |
| Precise Location | On the abdomen, level with the center of the umbilicus, in the depression at the lateral border of the rectus abdominis, normally 4 cun lateral to the anterior midline |
| Tissue Stimulated | Skin and subcutaneous tissue over the lateral edge of the rectus abdominis, the aponeurotic junction of the external oblique and internal oblique, and the underlying transversus abdominis, all within the T10 to T11 nerve field |
| Needle Depth / Direction | Perpendicular insertion approximately 0.5 to 1 cun, with some manuals citing up to about 1.2 cun in larger patients. Depth is reduced in thin patients because deeper needling can reach the peritoneal cavity, and it is reduced further when the spleen or liver is enlarged. Moxibustion is traditionally permitted. |
| De Qi Sensation | A dull, heavy, spreading fullness at the edge of the abdominal muscle, sometimes with a sense of pressure moving toward the midline or the flank. Intestinal gurgling during or after needling is common. Sharpness or radiating pain means the needle should be adjusted. |
| Primary Clinical Uses | Constipation (its signature modern use), sluggish and gassy digestion with distension, lower abdominal pain including cold-pattern diarrhea in classical use, abdominal wall tenderness at the rectus border, and in classical texts sighing with low mood |
| Common Point Combinations |
|
Deadman and colleagues' A Manual of Acupuncture presents Daheng as a point for regulating the qi of the Large Intestine, with traditional indications clustering into three groups: lower abdominal pain and cold-type or damp-type diarrhea, dysenteric disorder and constipation; heat sensation in the lower belly accompanied by sighing; and a curious set of systemic complaints including heaviness of the four limbs, copious sweating and a tendency toward sadness.
The same text notes that although SP15 and ST25 both serve intestinal disorders, clinical preference has long divided them, with ST25 leaning toward loose stools and SP15 toward constipation, and that SP15's ability to move intestinal qi is why it gets used across quite different causes of a blocked bowel. What stands out is the emotional column: SP15 appears in classical combinations for weeping and sighing without an obvious theoretical justification, though its abdominal neighbors ST23 and ST24 carry similar psycho-emotional listings.
Other manuals add the traditional actions of resolving damp, strengthening the Spleen and the limbs and stopping pain, and one classical selection principle even cites SP15 as an example of using a torso point for weakness of the extremities.
Taken together, the classical picture is of a point read as a lever on the whole middle of the body rather than a narrow bowel switch, which is striking given how narrowly it is used today.
Why SP15 Is Used for Sighing and Low Mood as Well as Constipation
The bowel use is easy to explain. SP15 sits directly over colon in a T10 to T11 segmental field, and the sensory nerves of the abdominal wall share dorsal horn neurons with visceral afferents from the gut. Needling that wall changes the input arriving at those shared neurons and triggers reflexes that reach the intestine through autonomic pathways. Animal work shows this is not random: stimulation of the abdomen and stimulation of the limbs drive different autonomic branches, and intensity matters, with stronger input required to produce reliable motility changes (Noguchi, 2008; Ma, 2020). That is exactly why clinicians combine an abdominal point like SP15 with a distal point like ST36 rather than relying on either alone.
The emotional indications are harder to pin down, but they are not absurd. Gut and mood run on a shared circuit: visceral afferents carry information to brainstem and limbic regions, chronic bowel symptoms drive anxiety and low mood, and stress reliably changes motility. Sighing, the symptom the classical texts kept recording next to SP15, is also a breathing pattern tied to diaphragm and abdominal wall tension. Needling that produces a slow, spreading sensation over the belly commonly relaxes guarded abdominal muscles and shifts breathing, which patients experience as feeling less braced.
On top of the local reflex, acupuncture engages descending inhibitory systems that use endogenous opioid, serotonergic and noradrenergic transmission to reduce nociceptive signaling (Zhao, 2008), and individual patient data across chronic pain conditions show effects that persist beyond the treatment period rather than fading immediately (Vickers et al., 2018). None of this proves the classical emotional indications, and we would not choose SP15 as a primary treatment for depression. It does, however, offer a plausible reason why a point over the gut can influence how a patient feels overall.
What the Research Shows for SP15
A caution before the table: almost no trial studies SP15 in isolation. Constipation and bowel research tests multi-point protocols, and the abdominal points used are usually ST25 and its immediate neighbors on the rectus abdominis, which occupy the same segmental territory as SP15 and are needled in the same tissue plane. What the literature can tell us is whether needling this region, combined with leg points, changes bowel outcomes. What it cannot tell us is how much any single point contributes.
| Study | Type | Focus | Key Finding |
|---|---|---|---|
| Liu et al., 2016 | Multicenter sham-controlled randomized trial (n = 1075) | Electroacupuncture at abdominal and leg points for chronic severe functional constipation | Eight weeks of electroacupuncture produced a larger increase in complete spontaneous bowel movements than sham, and the difference persisted through follow-up, though sham also improved. |
| Zhang et al., 2013 | Systematic review and meta-analysis | Acupuncture for chronic functional constipation | Acupuncture appeared broadly comparable to conventional therapy for bowel movement frequency, but the authors judged the evidence limited by small samples and methodological quality. |
| Manheimer et al., 2012 | Cochrane systematic review (17 trials, 1806 participants) | Acupuncture for irritable bowel syndrome | Sham-controlled trials did not show benefit over credible sham for symptom severity or quality of life, while comparisons against antispasmodic drugs favored acupuncture, a difference the authors attributed partly to expectation. |
| Noguchi, 2008 | Review of experimental physiology | Reflex regulation of gastroduodenal function by needling | In anesthetized animals, abdominal stimulation inhibited motility through sympathetic spinal reflexes while limb stimulation increased it through vagal pathways, with effects dependent on stimulation intensity. |
| Ma, 2020 | Narrative review of neuroanatomy | Somato-autonomic reflexes and acupoint selectivity | Body region and stimulation intensity appear to determine which autonomic pathway is recruited, offering a mechanistic account of why abdominal and limb points behave differently. |
Abdominal Wall Pain That Feels Like a Gut Problem?
Some belly pain comes from the abdominal wall itself, and tight rectus abdominis and oblique tissue can produce symptoms that mimic visceral complaints. Our clinicians assess the abdominal wall directly and combine acupuncture at points like SP15 with dry needling of the muscles that reproduce your pain. We coordinate with your gastroenterologist or primary care physician when that makes sense. Book an evaluation and we will map out what is muscular and what is not.
Schedule NowSP15 in the Context of Trigger Point Work
The great horizontal point sits exactly where clinicians palpate for abdominal wall tenderness, so acupuncture and dry needling overlap here almost completely. Trigger points in the rectus abdominis are documented as referring pain horizontally across the back at waist level and as producing visceral-seeming complaints such as bloating, nausea and a sense of abdominal fullness, while oblique trigger points can refer toward the groin and lower ribs (Simons et al., 1999).
When a patient's abdominal pain is reproduced by finger pressure on the muscle and not by anything the gastroenterologist can find, the abdominal wall itself deserves attention. Needling at SP15 in that setting is simultaneously a channel point and a myofascial target.
In practice we palpate the rectus border, the obliques and the transversus abdominis before deciding on technique. If taut bands and referred symptoms are present, we use dry needling into the involved muscle at a shallow, deliberate depth, then add SP15 with ST25 and a distal leg point when bowel regulation is also a goal. Depth stays conservative over the abdomen regardless of style, and we screen for hernia, mesh, organomegaly, pregnancy and undiagnosed abdominal pain first.
Patients often notice easier breathing and a looser belly wall before they notice any change in bowel habit, and both are useful signals that the tissue is responding.
SP15 Digestive Treatment at NYC's Highest-Rated Acupuncture Clinic
Morningside Acupuncture is the highest-rated acupuncture and dry needling clinic in New York City with over 500 five-star Google reviews, and digestive complaints are among the most common reasons patients come to us. We use SP15 (Daheng) within individualized protocols for constipation, bloating and stress-linked gut symptoms, always with clear expectations about what acupuncture can and cannot do. Sessions are unhurried, and we adjust the plan based on your response. Schedule your first appointment today.
Schedule NowFrequently Asked Questions
What does SP15 feel like when needled?
Most patients report a dull, heavy, spreading fullness at the outer edge of the abdominal muscle, sometimes with a mild ache traveling toward the navel or the flank. Because the point sits over the intestine, audible gurgling during the session is common and is a normal response rather than a problem. Sharp, burning or radiating sensations are not the target, and the needle should be repositioned if they occur.
Why needle the belly for constipation instead of only using points on the arms and legs?
Both approaches are used, and they appear to work through different routes. Experimental work shows that stimulating the abdominal wall drives segmental spinal reflexes that reach the gut through sympathetic pathways, while limb stimulation tends to recruit vagal pathways, with the effect depending on how strong the stimulation is (Noguchi, 2008; Ma, 2020). The abdomen also shares spinal segments with the colon, which is the anatomical reason a surface point at the navel can influence what happens underneath. In clinic we combine the two, which is exactly what the larger constipation trials did (Liu et al., 2016).
Can I press SP15 myself between sessions?
Yes, with common sense. Lie on your back with knees bent so the abdominal wall softens, find the level of your navel, then slide your fingertips outward about a hand's width until you feel the firm edge of the rectus muscle and drop just past it into the soft groove. Press with the pads of two or three fingers at a moderate, comfortable pressure for 30 to 60 seconds on each side, breathing slowly, then repeat with gentle circles for another minute or two. Doing this once or twice daily, often after breakfast, is reasonable. Skip it if you are pregnant, if you have unexplained or worsening abdominal pain, recent abdominal surgery, a known hernia or an enlarged liver or spleen, and see a physician instead if pain is new, severe or accompanied by fever, vomiting, bleeding or unintended weight loss.
Is SP15 safe to needle?
In trained hands, yes, with specific precautions. Classical guidance sets perpendicular insertion at roughly 0.5 to 1 cun and warns that in thin patients deeper needling can penetrate the peritoneal cavity, and that a substantially enlarged spleen or liver changes what lies beneath the point. Practitioners therefore palpate first, adjust depth to the individual rather than to a fixed number, and avoid the point over surgical mesh, unexplained masses or an acutely painful abdomen. Acupuncture over the abdomen is generally avoided during pregnancy. Acupuncture uses acupuncture needles regardless of the style being practiced, including dry needling, and the same anatomical cautions apply to all of them.
Where exactly is SP15 located?
SP15 (Daheng) is on the abdomen, level with the center of the umbilicus, in the depression at the lateral border of the rectus abdominis, normally 4 cun lateral to the midline. On the abdomen the 4 cun line and the outer edge of the rectus muscle correspond, so the muscle border is the practical landmark. Contract the abdomen briefly to feel the edge, then relax and let your finger settle into the groove just lateral to it. ST25 sits closer in at the same height, 2 cun from the midline, and SP14 lies a little more than a cun below SP15.
References
- Deadman, P., Al-Khafaji, M., & Baker, K. (2009). A manual of acupuncture. Journal of Chinese Medicine Publications.
- Cheng, X. (Ed.). (1999). Chinese acupuncture and moxibustion (Rev. ed.). Foreign Languages Press.
- Kim, H. (2008). Handbook of Oriental medicine (3rd ed.). Harmony & Balance Press.
- Maciocia, G. (2005). The foundations of Chinese medicine: A comprehensive text for acupuncturists and herbalists (2nd ed.). Elsevier Churchill Livingstone.
- Cunningham, P. M. (2000). Acupuncture points: A practical guide to classical and modern usage. Odyssey Press.
- Simons, D. G., Travell, J. G., & Simons, L. S. (1999). Travell & Simons' myofascial pain and dysfunction: The trigger point manual, Vol. 1: Upper half of body (2nd ed.). Williams & Wilkins.
- Liu, Z., Yan, S., Wu, J., He, L., Li, N., Dong, G., Fang, J., Fu, W., Fu, L., Sun, J., Wang, L., Wang, S., Yang, J., Zhang, H., Zhang, J., Zhao, J., Zhou, W., Zhou, Z., Ai, Y., ... Liu, B. (2016). Acupuncture for chronic severe functional constipation: A randomized trial. Annals of Internal Medicine, 165(11), 761-769. https://doi.org/10.7326/M15-3118
- Zhang, T., Chon, T. Y., Liu, B., Do, A., Li, G., Bauer, B., Wang, L., & Liu, Z. (2013). Efficacy of acupuncture for chronic constipation: A systematic review. The American Journal of Chinese Medicine, 41(4), 717-742. https://doi.org/10.1142/S0192415X13500493
- Manheimer, E., Cheng, K., Wieland, L. S., Min, L. S., Shen, X., Berman, B. M., & Lao, L. (2012). Acupuncture for treatment of irritable bowel syndrome. Cochrane Database of Systematic Reviews, 2012(5), CD005111. https://doi.org/10.1002/14651858.CD005111.pub3
- Noguchi, E. (2008). Mechanism of reflex regulation of the gastroduodenal function by acupuncture. Evidence-Based Complementary and Alternative Medicine, 5(3), 251-256. https://doi.org/10.1093/ecam/nem077
- Ma, Q. (2020). Somato-autonomic reflexes of acupuncture. Medical Acupuncture, 32(6), 362-366. https://doi.org/10.1089/acu.2020.1488
- Zhao, Z. Q. (2008). Neural mechanism underlying acupuncture analgesia. Progress in Neurobiology, 85(4), 355-375. https://doi.org/10.1016/j.pneurobio.2008.05.004
- Vickers, A. J., Vertosick, E. A., Lewith, G., MacPherson, H., Foster, N. E., Sherman, K. J., Irnich, D., Witt, C. M., & Linde, K. (2018). Acupuncture for chronic pain: Update of an individual patient data meta-analysis. Journal of Pain, 19(5), 455-474. https://doi.org/10.1016/j.jpain.2017.11.005
Disclaimer: This web site is intended for educational and informational purposes only. Reading this website does not constitute providing medical advice or any professional services. This information should not be used for diagnosing or treating any health issue or disease. Those seeking medical advice should consult with a licensed physician. Seek the advice of a medical doctor or other qualified health professional for any medical condition. If you think you have a medical emergency, call 911 or go to the emergency room. No acupuncturist-patient relationship is created by reading this website or using the information. Morningside Acupuncture PLLC and its employees and contributors do not make any express or implied representations with respect to the information on this site or its use. For any legal interpretation of scope of practice in your state, consult a licensed attorney or regulatory authority.
Read more from our blog



